What Is the Anion Gap?
The anion gap is a derived value that helps clinicians interpret electrolytes and assess acid-base balance. It is never a lab test by itself. Instead, it is a diagnostic aid derived from routine blood test results, usually from a standard serum chemistry or electrolyte panel.
At its core, the anion gap estimates the difference between the major measured positive and negative ions in the blood. Because some ions are not directly measured, the result can offer clues about anion concentration and the presence of unmeasured anions. That makes it especially helpful in the evaluation of an acid-base disorder, particularly when metabolic acidosis is suspected.
An anion gap calculator is simply a medical calculator that handles this calculation for you once the relevant lab values are entered. The result can assist in clinical interpretation, but it should always be considered alongside symptoms, the full metabolic panel, and other laboratory findings.
What Lab Values Does an Anion Gap Calculator Need?
To work out the anion gap, an anion gap calculator typically needs three core lab values: sodium, chloride, and bicarbonate. These measurements usually appear as serum sodium, serum chloride, and serum bicarbonate on a serum chemistry report.
These three measurements come from routine blood chemistry testing and are often included in a basic metabolic panel or comprehensive metabolic panel. Usually, the calculator uses the same numbers you would see on the lab report, so there is no special test beyond the standard blood draw.
Here is what each input contributes:
- Sodium: the chief measured cation used in the calculation. Chloride: the primary measured anion that is subtracted from sodium. Bicarbonate: a key buffer that reflects acid-base status and is also subtracted in the standard formula.
Since these are common measurements in a metabolic panel, the anion gap is easy to compute from everyday laboratory anion gap clinical significance data. Practically speaking, the calculator uses the values already available from a routine blood test, which makes it a quick way to assess electrolyte balance and possible disturbances in acid-base physiology.
How the Anion Gap Formula operates
The classic anion gap formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)This calculated result uses the observed ions existing in the blood, typically expressed in mEq/L. The formula illustrates the fact that the body maintains electrical neutrality, meaning positively charged and negatively charged substances must remain equal. However, not all ions are captured in routine lab work.
That is why the anion gap is valuable. It helps estimate the level of electrically charged ions not directly accounted for in the basic lab set. More help These hidden components are often referred to as unmeasured anions. When the gap shifts, it can suggest that something is affecting acid-base physiology or altering the equilibrium of measured and unmeasured substances.
A calculator makes this more straightforward by doing the arithmetic instantly. Still, understanding the calculation formula matters because the result depends entirely on the accuracy of the input values. If the sodium level, chloride level, or bicarbonate level is inaccurate, the anion gap will also be inaccurate.
Some clinicians also use a alternate version of the formula that includes potassium, but the standard approach does not require it. The basic version is the one most frequently used in routine clinical interpretation.
Reasons Why Albumin May Matter in Result Interpretation
While albumin is not part of the standard anion gap formula, it can greatly affect how the result is interpreted. Albumin is a negatively charged protein and a major contributor to the body’s overall electrical balance. When albumin is low, the anion gap may appear lower than expected even if a clinically important acid-base issue is present.
For this reason hypoalbuminemia matters. If albumin is reduced, the measured anion gap can underestimate the true burden of unmeasured acids. In that situation, clinicians may calculate an albumin-corrected anion gap to arrive at a better estimate of the underlying problem.
The correction is not always required, but it becomes more relevant when the patient has low protein levels, liver disease, malnutrition, inflammation, or critical illness. In those settings, the usual normal range may not reveal the full story.
For that reason, albumin is an important part of clinical interpretation even though it is not one of the three core inputs used by most anion gap calculators. A more complete assessment often includes the lab context, the overall electrolyte balance, and whether the patient may have a masked high anion gap due to low albumin.
Which Results Are Considered Normal vs Abnormal
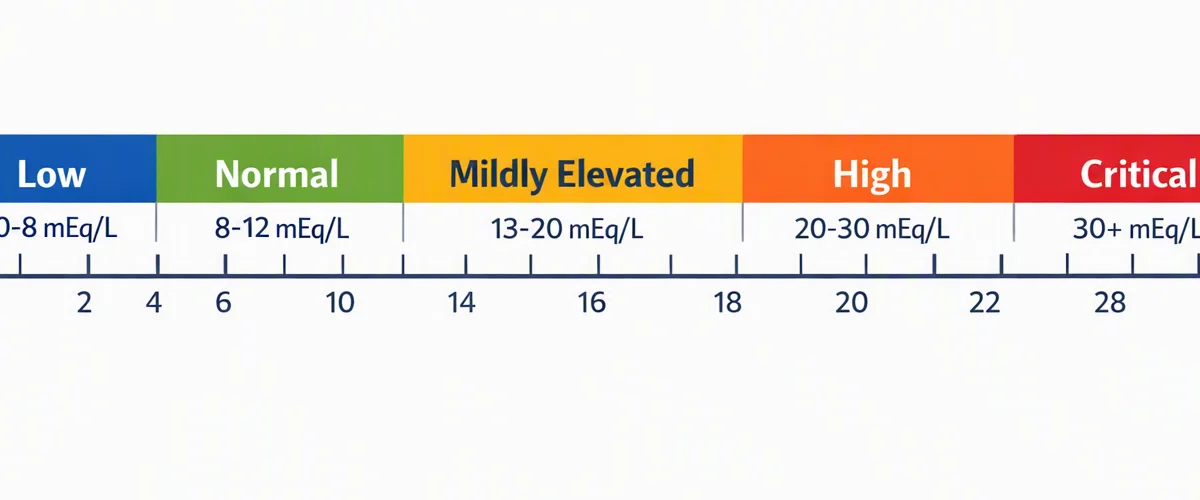
The normal anion gap varies somewhat with the laboratory and the analyzer used, so the reference range can vary. Many labs report a typical range that is narrow enough to guide interpretation but still slightly different from one system to another.
Overall, a result is considered:
- Normal anion gap: within the lab’s stated reference range. High anion gap: above the normal range and often associated with added unmeasured acids. Low anion gap: under the normal range and less frequent, sometimes due to protein changes or measurement issues.
A high anion gap is often the more significant finding because it may indicate a problem with acid handling, acid production, or acid clearance. A low value is usually interpreted with more caution because it is less often a sign of a primary disease process.
You should compare the result with the lab-specific normal range and the full clinical picture. The same number may be interpreted differently depending on the patient’s sodium, chloride, bicarbonate, albumin, and overall condition. This is where the clinical interpretation of the blood test matters more than the number alone.
Frequent Causes of a High Anion Gap
A increased anion gap often indicates a accumulation of acids that are not directly measured in the standard lab panel. This result is commonly seen in metabolic acidosis, especially when the body is producing too much acid or cannot remove it effectively.
Some of the most common causes consist of:
- Lactic acidosis: happens when lactate builds up, often in cases of poor oxygen supply, shock, severe illness, or intense physiologic stress. Ketoacidosis: develops when ketones rise, frequently in diabetes, prolonged fasting, or alcohol-related metabolic states. Kidney failure: decreases the body’s ability to remove acid and can cause retention of unmeasured anions.
Such conditions can raise the gap because they add to the amount of acids not included among the standard measured ions. The result may help guide clinicians toward the correct diagnosis, but it does not identify the cause on its own. Additional testing and clinical context are needed to determine whether the issue is lactic acidosis, ketoacidosis, kidney failure, or another process.
In practice, the anion gap is one part of the broader assessment of metabolic panel results. It helps sort the type of acidosis and determine whether the patient has a metabolic acidosis with an elevated gap or another acid-base pattern entirely.
FAQ
This section answers the most common questions about the anion gap calculator, the required lab values, and how various panels influence the result. This information can help you apply an electrolyte panel more effectively and see what the numbers mean.
Do You Need Potassium to Calculate It?
In most cases, no. The standard formula for the anion gap uses sodium, chloride, and bicarbonate only. Potassium is included in some versions of the calculation, creating a modified anion gap, but that is not the most common approach in routine clinical use. Most anion gap calculator tools rely on the standard formula unless they specifically say otherwise.
Can You Calculate an Anion Gap from a Basic Metabolic Panel?
Absolutely. A basic metabolic panel usually includes the values needed for the calculation: sodium, chloride, and bicarbonate. A comprehensive metabolic panel also includes those same values, so either lab test can provide the data needed for anion gap calculation. If the report includes the key electrolytes, the calculator can use them immediately.
What Causes a Low Anion Gap?
A low anion gap can happen for several reasons, including lab error, changes in chloride, or conditions such as multiple myeloma. Because low results are less common than high ones, they often prompt a careful review of the laboratory data and the patient’s overall condition. Low albumin can also contribute, so the result should be interpreted in light of other findings rather than in isolation.
What values are needed to calculate the anion gap?
You need three main lab values: serum sodium, serum chloride, and serum bicarbonate. An anion gap calculator uses those values to perform the standard calculation. In some cases, albumin may also be useful for interpretation, especially if the clinician is considering an albumin-corrected anion gap.
Can the calculator include potassium?
Most of the time, no. The common standard equation doesn't include potassium. A small number of calculators offer a modified anion gap that adds potassium, but that is not the typical method. When potassium matters, it is usually because the clinician wants a more specialized interpretation rather than a basic screening value.
Can you get the anion gap from a basic metabolic panel?
Yes. A basic chemistry panel often provides the necessary lab values, so it can be used to work out the anion gap. A comprehensive metabolic panel can be used as well because it includes the same electrolyte measurements. As long as the laboratory test reports sodium, chloride, and bicarbonate, the calculation can be done.
Why is albumin important when interpreting the anion gap?
Serum albumin plays a key role because it serves as a significant unmeasured anion. When albumin is decreased, especially in hypoalbuminemia, the calculated anion gap can seem incorrectly normal or low. In such situations, an albumin-corrected anion gap may better reflect the true acid-base status and help identify a hidden high anion gap.
What is a high or reduced anion gap mean?
A elevated anion gap commonly suggests metabolic acidosis due to conditions such as lactic acidosis, ketoacidosis, or kidney failure. A reduced anion gap is less common and may stem from lab error, protein abnormalities, or changes in chloride. The result should always be read using the full clinical picture and the laboratory’s normal range.