Understanding the Anion Gap
The anion gap is a derived value that helps assess the distribution of charged particles in the bloodstream, especially when evaluating electrolytes and acid-base balance. It contrasts the main measured positively charged ions, such as sodium, with the main measured negative ions, such as chloride and bicarbonate. Clinicians use it as a fast way to spot signs that may point to an acid-base disorder.
Although the anion gap is not directly measured, it is obtained from common lab data. That makes it a useful diagnostic tool in a blood test or serum chemistry panel. Because the body’s unmeasured ions also play a role to the total, the anion gap can reveal hidden imbalances in serum electrolytes even when individual values look only somewhat abnormal.
In plain terms, the anion gap helps judge whether there are extra acids in the bloodstream or whether bicarbonate has been lost. That is why it is often part of the metabolic panel used for clinical interpretation of symptoms like weakness, nausea, rapid breathing, or confusion.
How an Anion Gap Calculator Operates
An Anion Gap Calculator uses a straightforward anion gap formula using laboratory values from a serum chemistry panel. The standard form is:
Anion gap = sodium − (chloride + bicarbonate)
Some formulas also include potassium, especially in older formulas. In that case, the equation becomes sodium plus potassium minus chloride and bicarbonate. In most modern healthcare settings prefer the simpler version because potassium usually contributes less to the final result than the other components.
To calculate anion gap correctly, the calculator needs a current sodium level, chloride level, and bicarbonate level. These values come from routine serum electrolytes testing. https://anion-gap-help263.theglensecret.com/what-leads-to-normal-anion-gap-metabolic-acidosis The result then helps determine whether the pattern fits a normal anion gap or suggests another cause of acid buildup.

The calculator is most useful when it is paired with context. A number by itself does not explain everything. The same result can mean different things depending on the patient’s symptoms, medications, kidney function, hydration status, and overall clinical interpretation. That is why the calculator should be viewed as a guide, not a standalone diagnosis.
Typical Anion Gap Range Outlined
The usual range for the anion gap depends on the laboratory method and the local reference range. Different analyzers and calibration methods can produce slightly different values, so a result should always be read alongside the lab’s own normal interval. In many settings, a common range is roughly between 8 and 12 mEq/L when potassium is excluded, but the exact cutoffs can vary.
One reason the range varies is albumin. Albumin is a negatively charged protein that contributes to the unmeasured portion of the anion gap. If albumin is low, the measured gap may appear lower than expected even when the acid-base state is not truly normal. This is why albumin correction matters in certain cases.
A true normal anion gap usually suggests that there is no large accumulation of unmeasured acids. However, that does not automatically mean everything is normal. The result still needs to be interpreted in the context of base balance, kidney function, and other laboratory findings. A person may still have an illness even if the anion gap sits within the expected normal range.
For that reason, the anion gap should be seen as part of the broader picture of electrolyte status and test values, not as a single definitive answer.
Interpreting a Normal Anion Gap
A standard anion gap is especially important when assessing metabolic acidosis. If bicarbonate is low but the anion gap stays normal, the pattern often points to metabolic acidosis without an elevated anion gap. In this scenario, the body has depleted bicarbonate or kept chloride rather than accumulating a large amount of unmeasured acid.
Two common causes are renal tubular acidosis and digestive bicarbonate loss. Renal tubular acidosis occurs when the kidneys do not manage acid and bicarbonate properly. Gastrointestinal bicarbonate loss can happen with prolonged diarrhea or other digestive fluid losses. Both can lower bicarbonate while keeping the anion gap in the normal range.
Interpreting this result correctly is vital for a proper workup for metabolic acidosis. A normal gap can help limit the differential diagnosis and direct further testing. It may prompt review of urine studies, kidney function, medication use, and fluid losses. In other words, the pattern matters as much as the number.
One useful way to think about it is this: when the anion gap is normal, the problem often lies in bicarbonate loss or chloride gain rather than hidden acid accumulation. That distinction is key to medical interpretation and helps clinicians determine the most likely source of the disorder.
Elevated Anion Gap vs Normal Anion Gap
A high anion gap indicates that unmeasured acids are building up in the circulation. This remains in contrast to a typical gap pattern, where bicarbonate loss or chloride retention is more likely. Recognizing this contrast is one of the key reasons people use an Anion Gap Calculator when reviewing an electrolyte panel.
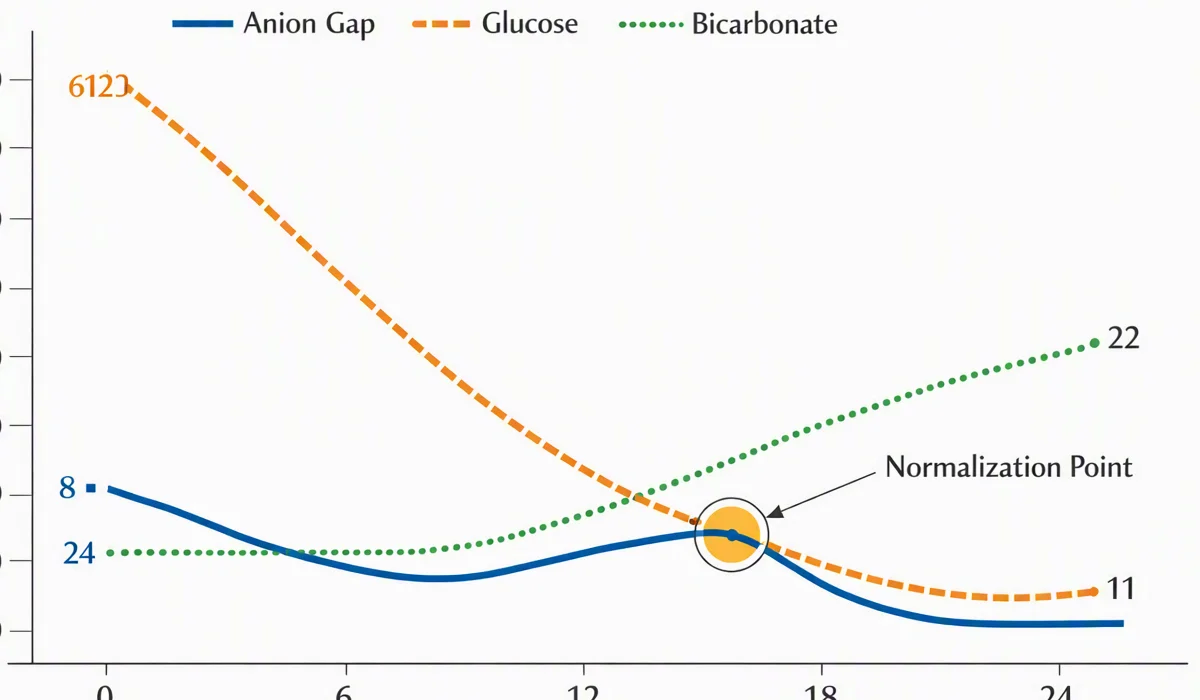
Frequent causes of a high anion gap include lactic acidosis, ketoacidosis, and toxic ingestions. Lactic acidosis may occur when tissues do not get enough oxygen or when metabolism is disrupted. Ketoacidosis can happen in uncontrolled diabetes, starvation, or alcohol-related illness. Toxic ingestions may involve substances that create acid or interfere with metabolism.
By contrast, a typical result points away from those classic high-gap causes and toward patterns such as non-anion gap metabolic acidosis. This comparison is clinically important because the next steps in care may differ substantially. For example, a high gap often leads to a search for acid overproduction or toxin exposure, while a normal gap may shift attention to renal or gastrointestinal losses.

Because of this difference, the anion gap is not just a number. It is a organized way to arrange electrolyte abnormalities and support quicker, more focused decision-making.
Elements Influencing the Calculation
Various conditions can change the calculation even when the original condition has not varied greatly. One major factor is hypoalbuminemia. Since albumin carries negative electrical charge, low levels can decrease the measured gap. In that setting, a corrected anion gap can offer a more precise picture of the acid base state.
Measurement units also count. The calculator assumes uniform lab units, and mixing units can cause misleading numbers. A slight change in the reporting format may yield a very different-looking result if it is entered incorrectly. That is one reason the Anion Gap Calculator should be used cautiously and verified against the actual lab report.
Lab error is another possible source of confusion. Sample handling, analyzer variation, and transcription mistakes can all influence the final number. If the result does not fit the clinical picture, repeating the blood test may be advisable.
Because of these caveats, a low or seemingly normal value should not be interpreted in isolation. A corrected anion gap may be more informative when albumin is abnormal, and the overall clinical picture should always inform the next step.
When to Use an Anion Gap Calculator
An Anion Gap Calculator is most useful when a clinician is reviewing a blood test or electrolyte panel and needs help interpreting possible acid-base changes. It is particularly helpful when bicarbonate is low, when there are unexplained symptoms, or when the cause of an acid-base disorder is not obvious.
It can be used during a general clinical assessment to aid faster pattern recognition. For example, if a patient has abnormal serum electrolytes on a serum chemistry panel, the calculator can help determine whether the pattern fits high-gap acidosis, normal-gap acidosis, or another imbalance. This makes it a useful part of bedside reasoning and laboratory review.
The calculator is also useful when reviewing serial labs over time. Changes in the anion gap may help show whether treatment is working or whether a condition is evolving. In that sense, it is not just a one-time number but a way to track electrolyte balance and acid-base trends.
Still, the calculator should support, not replace, a full medical evaluation. Symptoms, medications, kidney function, blood sugar, lactate, ketones, and albumin all matter. The best use of the tool is as one piece of a larger diagnostic process.
FAQ
What is considered a normal anion gap value?
A normal anion gap value depends on the lab’s reference range and the method used to measure serum electrolytes. Most labs use a range around 8 to 12 mEq/L without potassium, but the exact expected range can vary. Always interpret the result using the lab’s own reference interval.
How do you calculate the anion gap?
The standard formula for anion gap is sodium minus the sum of chloride and bicarbonate. Some calculations also include serum potassium. An Anion Gap Calculator computes this value automatically using values from a blood chemistry panel. To determine the anion gap accurately, the input values must be correct and in the proper units.
What does a normal anion gap suggest?
A normal result often means there is no major accumulation of unmeasured acids. In the setting of low bicarbonate, it may suggest hyperchloremic metabolic acidosis rather than a high-gap process. Common causes include RTA and loss of bicarbonate from the gut. The result still needs full medical interpretation in context.
What are the causes of normal anion gap metabolic acidosis?
Common causes include renal tubular acidosis, loss of bicarbonate from the gut, and some forms of kidney dysfunction or medication-related acid-base changes. In these cases, bicarbonate is reduced, but the gap stays normal because chloride often rises to maintain balance. This pattern is a classic part of the evaluation of metabolic acidosis.
Why does albumin affect the anion gap?
Serum albumin is a negatively charged protein that contributes to the unmeasured portion of the gap. When albumin is low, the anion gap may appear artificially lower, which is why decreased albumin can mask a problem. A albumin-corrected anion gap helps account for this and gives a more accurate estimate of the true acid-base status.