What Does Mean the Anion Gap?
This anion gap acts as a derived value that helps healthcare providers evaluate acid-base balance by weighing the major measured cations and anions in the blood. It is commonly obtained from routine serum electrolytes, especially sodium, chloride, and bicarbonate. Because the body must maintain electrical neutrality, the anion gap estimates the difference between measured positively charged and negatively charged particles, indirectly showing unmeasured ions.
In practical terms, the anion gap is especially useful when evaluating metabolic acidosis. A shift in the gap often points toward excess acids, lost bicarbonate, or laboratory patterns that require a broader diagnostic approach. Because it relies on common laboratory values, it is one of the simplest tools for recognizing an acid-base disorder and limiting the differential diagnosis.
Although the exact number can vary based on the lab’s reference range, a normal result usually suggests that measured cations and anions are in expected balance. A higher-than-expected result can indicate high anion gap acidosis, while a normal value in the setting of acidosis may indicate normal anion gap or hyperchloremic processes. That distinction is central to clinical interpretation.
How the Anion Gap Calculator Works
An anion gap calculator automates the anion gap formula so that clinicians can promptly interpret laboratory values and evaluate for an electrolyte imbalance. The classic formula is:
Anion gap = sodium − (chloride + bicarbonate)
Some versions use potassium, but most bedside interpretation relies on the streamlined formula above. The calculator uses serum sodium, serum chloride, and serum bicarbonate to determine the amount of unmeasured anions in the plasma. A higher gap usually suggests presence of organic acids or other unmeasured substances.
The calculator becomes even more helpful when albumin is abnormal. Because albumin is a negatively charged protein and a major unmeasured anion, low albumin can make the gap appear falsely normal. That is why many clinicians apply albumin correction before final interpretation. The output is often a corrected anion gap, which gives a more accurate picture of the patient’s underlying acid-base status.
In real-world use, the calculator supports rapid blood gas analysis and complements the exam of acid-base patterns. It does not replace clinical judgment, but it helps with the first step in recognizing metabolic acidosis, especially when the cause is not immediately obvious.
Why the Anion Gap Matters in Acid-Base Balance
The anion gap matters because it assists in distinguishing different kinds of acid-base balance problems. When metabolic acidosis is present, the gap can suggest either a high anion gap or a normal anion gap profile. This difference is important because the causes, urgency, and treatment strategies are often different.
In high gap acidosis, the body has https://anion-gap-formula708.bearsfanteamshop.com/what-are-undetected-anions-in-blood accumulated unmeasured acids. In normal gap acidosis, bicarbonate is often lost and replaced by chloride, which preserves the gap but still produces acidemia. This is why the anion gap is not just a number; it is a framework for understanding the underlying buffering system and how the body reacts to an acid-base disorder.
It also helps identify a mixed disorder. For example, a patient may have a metabolic acidosis and a second process affecting pH, such as respiratory compensation that is inadequate or exaggerated. In these cases, the anion gap adds clarity to the clinical interpretation of the patient’s labs and symptoms.
Because the gap is tied to measured and unmeasured ions, it is a helpful connection between routine chemistry testing and deeper physiologic reasoning. That makes it a key tool in both routine medicine and urgent evaluation.
How to Interpret a Increased Anion Gap
A high anion gap usually means that undetected acids are present in greater amounts. This is a typical finding in various important causes of metabolic acidosis, and it should trigger a targeted search for the source of the acid load.
Typical causes include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. In lactic acidosis, tissue reduced blood flow, sepsis, seizures, or intense physiologic stress can increase lactate production. In ketoacidosis, ketone bodies build up when insulin is lacking or when starvation and alcohol-related states alter metabolism. Renal failure can impair acid excretion, allowing unmeasured acids to collect. Toxic alcohol ingestion is another major cause because substances such as methanol or ethylene glycol generate acid metabolites that raise the gap.
When the gap is high, the next question is not just “Is it high?” but “Why is it high?” That requires correlating the anion gap with the patient’s history, exam, and other lab data. A patient with acidemia, elevated lactate, and hypotension may have lactic acidosis. Someone with hyperglycemia or starvation may indicate ketoacidosis. Kidney function tests, osmolar calculations, and toxicology clues may be needed in other scenarios.
A high gap is especially concerning because it can signal a urgent condition that needs rapid treatment. The anion gap calculator helps detect the pattern early, but the clinician must then relate it to the patient’s overall presentation.
How to Read a Normal Anion Gap
A normal anion gap does not exclude metabolic acidosis. Instead it usually suggests reduced bicarbonate with a reactive elevation in chloride, causing chloride-related acidosis. This is commonly described as normal-anion-gap acidosis.
A very common cause is gastrointestinal fluid loss, where the body loses bicarbonate-rich intestinal fluid. Another key cause is renal tubular acidosis, in which the kidneys do not process acid or bicarbonate normally. In either case, the drop in bicarbonate is central, but the anion gap remains in the expected range because chloride rises to preserve electroneutrality.
This picture can be simple to miss if attention is placed only on the pH. A patient may be acidemic with low bicarbonate but still have a normal gap. This is why, a full review of electrolyte values matters. The chloride level level often goes up relative to bicarbonate, creating the lab pattern that supports a normal-gap process.
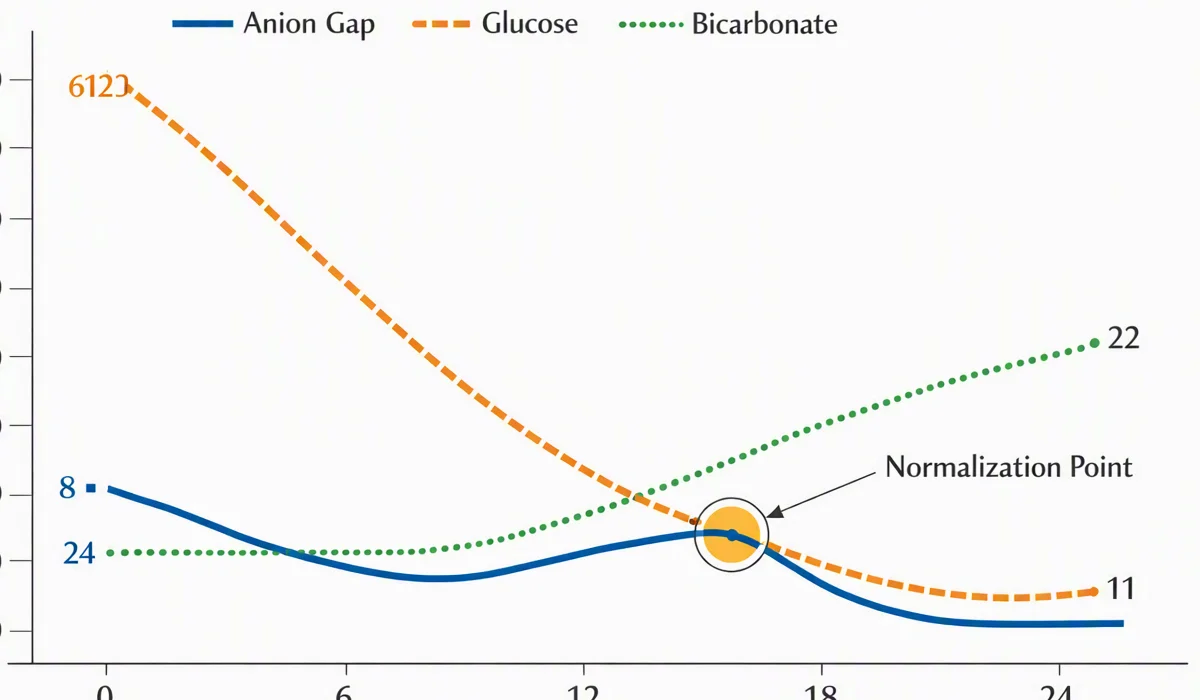
Normal-gap patterns are also useful when evaluating treatment effects. For example, after a high-gap acidosis begins to resolve, the gap may normalize while bicarbonate remains low, or the patient may develop a mixed picture. Careful tracking prevents misclassification and supports better medical interpretation.
Albumin Correction and Additional Important Corrections
Albumin is among the most important elements to consider when interpreting the anion gap. Because albumin contributes substantially to the pool of unmeasured anions, hypoalbuminemia can lower the measured gap and obscure a clinically significant acidosis. In these cases, albumin correction is necessary.
The resulting corrected anion gap gives a better picture of the true acid burden. Without this adjustment, a patient may appear to have a normal gap even when a high-gap process is present. This is especially important in ill patients with inflammation, malnutrition, liver disease, or critical illness, where low serum albumin is common.
Albumin’s role is tied to protein binding and the overall charge balance in plasma. When albumin falls, the baseline anion gap falls too. That means the lab result has to be interpreted in context rather than as an isolated number. A clinician using an anion gap calculator should therefore check whether the tool includes an albumin adjustment or whether correction must be done separately.
Other adjustments may also matter depending on the setting, but albumin is the major one in routine practice. It is a reminder that not all “normal” results are truly normal. If the patient has hypoalbuminemia, a corrected value may reveal hidden high gap acidosis that changes the differential diagnosis and treatment priorities.
Step by Step: How to Determine Acid-Base Status
A useful method begins with the complete data set: serum electrolytes, an arterial blood gas, and the patient's clinical presentation. The aim is to identify whether there is acidemia or alkalemia, whether the problem is metabolic or respiratory, and whether the anion gap helps explain the pattern.
First, review the pH on the blood gas. If the pH is low, acidemia is present. Next, examine bicarbonate and carbon dioxide to decide whether the primary problem is metabolic or respiratory. If bicarbonate is low, metabolic acidosis is likely. At that point, calculate or review the anion gap using sodium, chloride, and bicarbonate.
Second, assess whether respiratory compensation is appropriate. The lungs often reduce carbon dioxide in response to metabolic acidosis. If compensation is not as expected, another process may be present. This is where blood gas analysis and the electrolyte panel should be interpreted together rather than separately.
After that, decide whether the pattern is high-gap or normal-gap. A high-gap pattern should trigger evaluation for lactic acidosis, ketoacidosis, renal failure, or toxic alcohol exposure. A normal-gap pattern should raise suspicion for diarrhea, renal tubular acidosis, or other sources of bicarbonate loss.
Finally, review whether albumin is low and whether a corrected anion gap is needed. This step improves accuracy and can reveal a mixed disorder that would otherwise be overlooked. In short, the process is: assess pH, identify the primary disorder, calculate the gap, correct for albumin, and then interpret the result in context.
Typical Pitfalls in Anion Gap Interpretation
A single of the main errors is overlooking lab error or collection issues. A single abnormal result should always be be checked against the rest of the panel and the clinical picture. If the numbers do not make biologic sense, repeat testing may be needed before drawing conclusions.
One more error is overlooking the reference range used by the laboratory. Various analyzers and institutions may have somewhat different normal ranges, so the same numeric result can be interpreted with a different meaning depending on the setting. This is why the anion gap should never be treated as a single diagnosis.
It can also be easy to miss a mixed acid-base disorder. As an example, a patient may have a high anion gap and a coexisting metabolic alkalosis, or a normal gap with a respiratory process overlapping. The delta gap is useful here because it compares the change in the anion gap to the change in bicarbonate and can suggest whether additional processes are present.
Another common pitfall is forgetting that low albumin changes the baseline. If hypoalbuminemia is present, the measured anion gap may fail to reflect the severity of the disturbance. Thoughtful albumin correction minimizes this risk and improves diagnostic precision.
When You Should Use an Anion Gap Calculator
An anion gap calculator is particularly useful when a rapid, accurate assessment is needed for clinical decision making. It is particularly valuable during emergency evaluation when a patient presents with vomiting, altered mental status, shock, dyspnea, or signs of acidemia. In these situations, rapid recognition of an acid-base disorder can influence immediate care.
The calculator is also important in critical care, where serial labs are reviewed repeatedly and subtle changes can matter. Patients with sepsis, kidney dysfunction, diabetes, intoxication, or gastrointestinal losses often have changing electrolyte patterns. A calculator helps structure those values into a clear interpretation.
In routine practice, the tool facilitates a more structured approach to any suspected acid-base disorder. It can help differentiate metabolic acidosis from other problems, identify when albumin correction is needed, and guide next-step testing. Because it links electrolytes, albumin, and the broader clinical picture, it is not just a math aid; it is part of the diagnostic workflow.
To get the best results, use it alongside the patient’s symptoms, medications, kidney function, glucose, lactate, ketones, and blood gas results. That broader context turns a number into practical guidance.
Frequently Asked Questions About Anion Gap and Acid-Base Balance
What is the anion gap and why is it important?
The anion gap is a computed value from sodium, chloride, and bicarbonate that helps assess acid-base balance. It is important because it helps detect metabolic acidosis and distinguish between high anion gap and normal anion gap patterns, which have distinct causes and treatment priorities.
How do you calculate the anion gap from lab values?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate: sodium − (chloride + bicarbonate). An Anion Gap Calculator performs this calculation automatically using serum electrolytes. If albumin is low, albumin correction may be needed for a more precise result.
What does a high anion gap mean in acid-base balance?
A high anion gap usually means there are additional unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohol ingestion. It often signals a medically significant form of metabolic acidosis that needs prompt evaluation.
How does low albumin affect the anion gap?
Hypoalbuminemia decreases the reported anion gap because albumin is a key unmeasured anion. That can cause a true high-gap process appear normal. Using a corrected anion gap helps account for this effect and improves clinical interpretation.
Can a normal anion gap still occur with metabolic acidosis?
Yes. A normal anion gap can still be seen with metabolic acidosis, especially when there is bicarbonate loss replaced by chloride. Common causes include diarrhea and renal tubular acidosis, often described as hyperchloremic acidosis or normal gap acidosis.