Understanding the Anion Gap?
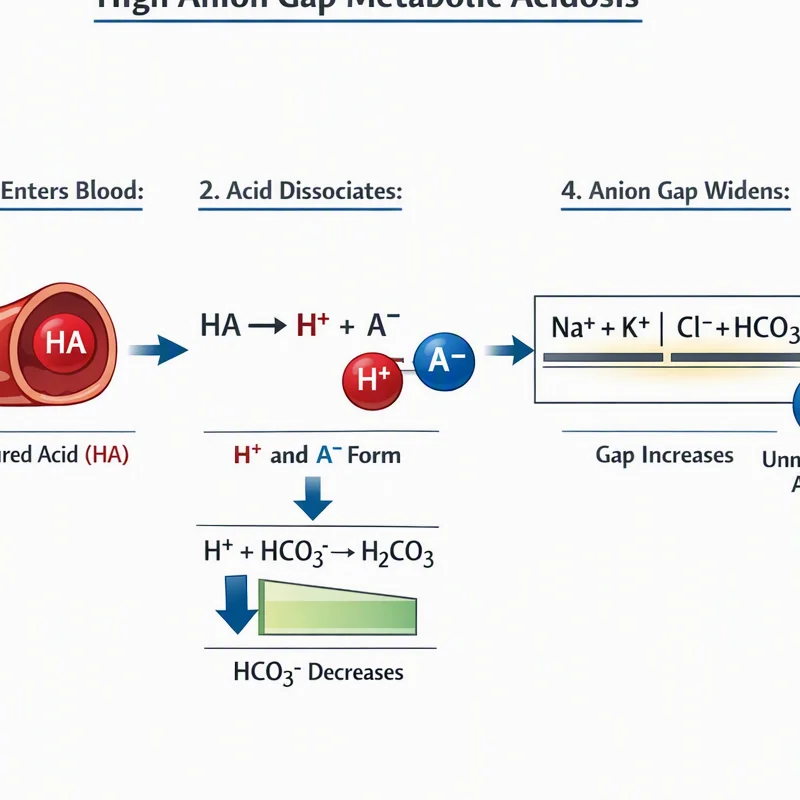
The anion gap is a calculated value that helps assess the balance of charged particles in the blood. It is calculated from routine serum electrolytes and is often used as a diagnostic marker in acid-base imbalance evaluation. The most common version uses sodium, chloride, and bicarbonate to determine the difference between measured ions and unmeasured electrolytes.
In simple terms, the anion gap contrasts the positively charged and negatively charged components found in standard blood chemistry. Because not every ion is directly measured, the gap can reveal hidden acids or other substances that may be affecting the body’s acid-base state. This makes it especially useful in metabolic acidosis workups.
The standard formula for the anion gap is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some clinicians include potassium in the equation, but the most widely used version leaves it out. The result is usually expressed in mEq/L, and interpretation depends on the lab’s expected range or the expected range used by the clinician.
Why Fix the Anion Gap for Albumin?
Albumin is one of the main anion-carrying proteins in blood, so it has a major effect on the calculated anion gap. When albumin is low, the measured gap can look falsely normal or low even when a genuine acid-base problem is present. This is why hypoalbuminemia counts so much during acid-base interpretation.
Correcting the gap for albumin improves accuracy because it accounts for the reduced negative charge contributed by low serum albumin. In other words, the corrected anion gap gives a more realistic picture of the body’s acid load. This is especially important in patients with illness, inflammation, malnutrition, liver disease, or other conditions that reduce albumin.
A standard albumin correction factor is used to estimate how much the gap should go up when albumin is below normal. The goal is to make the adjusted result more trustworthy for clinical decision-making. This is why an anion gap calculator often includes albumin as an input field.
Revised Anion Gap Equation
The usual anion gap formula reads:
Anion gap = Sodium − (Chloride + Bicarbonate)
To work out the albumin-corrected anion gap, include an adjustment for reduced albumin. A widely used albumin correction is written as:
Corrected anion gap = Measured anion gap + 2.5 × (4.0 − albumin in g/dL)
This formula uses 4.0 g/dL as a normal normal albumin value and adds 2.5 mEq/L for every 1 g/dL decrease in albumin below 4.0. The exact factor can change somewhat by source, but this version is widely used in practice. Always interpret the result using your lab’s normal range and the clinical context.
If potassium is used in a local protocol, the equation is expressed as:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
However, most calculators and clinical references rely on the sodium-based formula. The corrected value is still reported in mEq/L, and the purpose is to better identify a hidden high anion gap state when albumin is low.
Step by Step: How to Calculate Corrected Anion Gap
To calculate corrected anion gap by hand, use the basic laboratory results from the electrolyte panel. You need serum sodium, serum chloride, serum bicarbonate, and albumin level. These are all common laboratory values reported on routine blood tests.
Follow this step-by-step formula:
- Step 1: Find the raw anion gap using sodium − (chloride + bicarbonate). Step 2: Check the albumin result with the normal value, usually 4.0 g/dL. Step 3: Multiply the albumin deficit by the albumin correction factor, usually 2.5. Step 4: Insert that number to the raw anion gap. Step 5: Review the corrected result with the expected range.
Worked example:
Raw anion gap = 140 − (104 + 24) = 12 mEq/L
Albumin correction = 2.5 × (4.0 − 2.0) = 5 mEq/L
Corrected anion gap = 12 + 5 = 17 mEq/L
This basic clinical calculation can change the interpretation significantly. A raw value that looks normal may turn elevated once albumin is accounted for.
How an Anion Gap Calculator Works
An anion gap calculator is an internet calculator or healthcare calculator that handles the math for you. It usually includes input fields for sodium, chloride, bicarbonate, and albumin. Some versions also allow potassium, although it is not always necessary.
The calculator analyzes the lab values, applies the anion gap correction, and displays a corrected result. This makes it quicker to evaluate blood chemistry in clinical settings where a quick result analysis is helpful. It also reduces the chance of arithmetic mistakes during busy workflows.
Most calculators display both the raw gap and the albumin-corrected anion gap. That dual output helps clinicians review the unadjusted and adjusted numbers side by side. For users learning the concept, the calculator can also work as an interpretation guide by showing whether the result falls into a normal or elevated range.
Interpreting a High or Normal Corrected Anion Gap
A elevated anion gap usually suggests the presence of excess additional anions. This is a important clue in metabolic acidosis assessment. Common causes include lactic acidosis, ketone-driven acidosis, kidney failure, and toxic exposures.
If the corrected value is high, the clinician should suspect a hidden acid load is present even if the raw gap looked normal. This is why the corrected number is such an important diagnostic marker. Low albumin can mask the severity of the acid-base problem, and albumin correction helps unmask it.
A normal corrected anion gap after correction may suggest that the raw elevation was mostly explained by low albumin. That does not rule out disease, https://pastelink.net/u7eyozxk but it changes the interpretation. In contrast, a persistently high corrected result suggests a true acid excess and may guide the next steps in the metabolic acidosis workup.
Useful interpretation points:
- High corrected gap: consider hidden acids or excess unmeasured ions. Normal corrected gap: the apparent elevation may be explained by hypoalbuminemia. Low albumin can allow a dangerous process look less abnormal than it really is.
Common Errors in Calculating the Corrected Anion Gap
One common error is a measurement conversion problem. Albumin may be reported in g/dL or g/L depending on the lab, and the formula only works correctly with the intended unit. Using the wrong unit can distort the result and produce a misleading number.
A further concern is using the wrong normal range. Different laboratories may list slightly different normal intervals for anion gap, so the same number can be interpreted differently depending on the lab’s standards. Always compare the result with the local normal range.
Some people also forget to consider whether potassium is included. If a formula includes potassium in one setting but not another, the values will not match. That mismatch is a frequent calculation error in hand calculations and in copied notes.
Common errors include:
- Calculating with the raw gap without albumin adjustment when albumin is clearly low. Using bicarbonate instead of total CO2 without understanding the lab report. Expecting every calculator uses the same correction factor. Overlooking the clinical context of the blood chemistry.
A careful review of the inputs prevents misleading conclusions and improves the quality of the final interpretation.
Samples of Revised Anion Gap Calculations
Here is a sample calculation based on standard lab values. Assume:
- Sodium = 138 mEq/L Chloride = 104 mEq/L Bicarbonate = 22 mEq/L Albumin level = 2.4 g/dL
First, work out the initial anion gap:
138 − (104 + 22) = 12 mEq/L
Next, determine the albumin correction:
2.5 × (4.0 − 2.4) = 4.0 mEq/L
Afterward, add the correction to the initial anion gap:
Corrected value = 12 + 4 = 16 mEq/L
This means that the adjusted result is increased even though the raw anion gap was in many labs’ normal range. The low albumin was hiding part of the abnormality.
One more worked example:
- Sodium = 142 mEq/L Serum chloride = 100 mEq/L Bicarbonate = 26 mEq/L Albumin level = 4.2 g/dL
Raw anion gap = 142 − (100 + 26) = 16 mEq/L. Because albumin is not low, very little correction is needed. The adjusted value remains basically the same, and the elevated gap is more prone to reflect a real increase in unmeasured acids.
When to Consider a Corrected Anion Gap in Clinical Practice
A anion gap clinical significance corrected gap is especially useful when the patient has hypoalbuminemia and an acid-base disorder is being evaluated. It is particularly helpful in critical care, where fluid shifts, inflammation, malnutrition, and organ dysfunction often lower albumin. In those cases, the raw result can be misleading.
It also matters in kidney disease, where acid retention can change the electrolyte pattern and complicate interpretation. A corrected value can improve the diagnostic picture and help clinicians distinguish between different causes of acidosis.
Another important use is toxic ingestion evaluation. If a patient has unexplained acidosis, an elevated corrected gap may support the presence of hidden acids or toxic compounds. That can change urgent management decisions.
In routine interpretation, apply the corrected value if:
- Albumin is below normal. You are concerned about metabolic acidosis. The raw anion gap seems unexpectedly normal or borderline. Clinical findings do not match the measured electrolyte pattern.
In this context, the corrected value becomes a useful reference tool rather than just another number.
FAQ About Anion Gap Calculation
How can you calculate corrected anion gap from lab values?
First of all compute the original anion gap using sodium − (chloride + bicarbonate). Next modify for albumin using an albumin correction factor, usually 2.5 mEq/L for each 1 g/dL albumin below 4.0. This produces the corrected anion gap, which offers a better clinical calculation when albumin is low.
Why does albumin change the anion gap?
Serum albumin is a major negatively charged protein in blood, so reduced albumin levels reduces the number of unmeasured negative charges. This may make the calculated anion gap seem lower than it really is. Albumin adjustment helps restore the typical range and enhances acid-base interpretation.
What’s the usual corrected anion gap range?
The typical albumin-corrected anion gap value range depends on the laboratory’s benchmark range, but many clinicians expect it to stay within the typical anion gap range of values after albumin correction. Because methods differ, always interpret the result using the lab’s normal range and the patient’s full clinical picture.
Should potassium be included in the anion gap calculation?
In most cases, potassium is not part of the standard formula employed by most anion gap calculator tools. Certain formulas do include potassium, but that is less common. If potassium is included, the result will change, so the method must be in line with the reference or calculator you are using.
When is it appropriate to use a corrected anion gap be used instead of the raw anion gap?
Apply adjusted anion gap whenever albumin is decreased and you are evaluating an acid–base disorder, especially a metabolic acid buildup. The corrected value is more accurate in hypoalbuminemia because it accounts for hidden changes in undetected ions. It is especially useful in critical care, kidney disease, and toxic ingestion workups.