How the Anion Gap Shows
The anion gap is a calculated value used in acid-base status assessment to help identify an electrolyte imbalance or a underlying acid-base disorder. It contrasts the major measured cations and anions in the blood and provides clinicians a clue about the presence of unmeasured anions that may be contributing to a metabolic disturbance.
In standard practice, the anion gap is calculated from a serum chemistry or electrolyte panel, especially from serum sodium, serum chloride, and serum bicarbonate. These values represent the balance of charged particles in the bloodstream and are part of the body’s buffer system. When the balance shifts, the anion gap can help narrow the differential diagnosis.
Clinically, the anion gap is a useful biochemical marker during clinical assessment and patient evaluation. It does not diagnose a condition by itself, but it can signal that blood test results need additional review. An elevated gap often points toward high anion gap metabolic acidosis, while a normal result may still be informative depending on the broader picture.
How an Anion Gap Calculator Operates
An anion gap calculator is a basic diagnostic tool that carries out the anion gap calculation from routine lab values. Most calculators use the anion gap formula:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some versions also include potassium, but numerous modern calculations omit it because the contribution of potassium is limited in typical routine settings. In those cases, the formula becomes more concise and simpler to apply from a standard blood chemistry result.
The calculator depends on a complete blood chemistry panel or electrolyte panel. A clinician or patient inputs the measured values for sodium, chloride, and bicarbonate, and the calculator outputs the anion gap. The result can then be compared with the expected reference interval or reference range used by the laboratory.
This process is straightforward, but interpretation requires context. A single number does not replace laboratory interpretation or clinical judgment. The calculator is especially helpful when paired with the rest of the serum chemistry, the patient’s symptoms, and other diagnostic data.
Normal Anion Gap compared with Elevated Anion Gap
A standard anion gap often indicates that if acidosis is present, it may be due to reduction of bicarbonate rather than accumulation of unmeasured acids. In contrast, a elevated anion gap indicates that additional acids are present in the blood, commonly leading to metabolic acidosis.
Because the usual range can fluctuate between laboratories, the exact cutoff should be interpreted using the lab’s own reference interval. This is especially important when evaluating acid-base status in hospitalized patients or in critical care settings, where small changes can matter.
Albumin serves a major role in the interpretation of the anion gap because it is a negatively charged protein. When albumin is low, the measured anion gap may appear falsely normal or only mildly elevated. That is why a normal reading does not always exclude an acid-base disorder.
In practical terms, an elevated anion gap often points to increased acids, while a normal anion gap may reflect bicarbonate loss, chloride anion gap clinical significance retention, or a mixed disturbance. Understanding the pattern helps clinicians evaluate the result in relation to the patient’s overall clinical assessment.
Frequent Causes of High Anion Gap Metabolic Acidosis
High anion gap metabolic acidosis occurs when acidic substances collect more quickly than the body can neutralize or eliminate them. A number of common causes should be considered during differential diagnosis.
Lactic acidosis happens when lactate builds up, often due to reduced tissue oxygen delivery, sepsis, shock, seizures, or serious illness. It is a major cause of an increased anion gap in emergency and inpatient environments.
Ketoacidosis is an additional classic cause. It can occur in diabetic ketoacidosis, starvation, or alcohol-related ketosis. In this setting, ketone bodies act as unmeasured anions and increase the gap.
Reduced kidney function can also raise the anion gap because impaired kidney function reduces acid excretion and allows organic acids to accumulate. Reviewing renal function alongside electrolyte values is essential for a complete evaluation.
Toxic alcohol ingestion, such as methanol or ethylene glycol, are important to consider when the clinical picture suggests poisoning. These substances generate acidic metabolites and can produce a dangerous metabolic disturbance. They are a urgent diagnosis and often require urgent treatment.
Other contributors may include advanced liver disease, certain medications, or severe tissue injury. The exact cause depends on the pattern of symptoms, the serum chemistry profile, and the broader medical context.
How to Read Results in Medical Context
The value from an anion gap calculator is especially useful when considered alongside the complete clinical picture. One value cannot define the cause of illness, but it can support medical decision-making and clarify whether further testing is needed.
If the patient has signs of metabolic acidosis, an elevated gap may indicate that acid is accumulating. An arterial blood gas can then help toxic causes elevated AG confirm the acid-base pattern and show whether there is respiratory compensation. For example, a low pH with low bicarbonate and an elevated gap points to a primary metabolic process rather than a purely respiratory one.
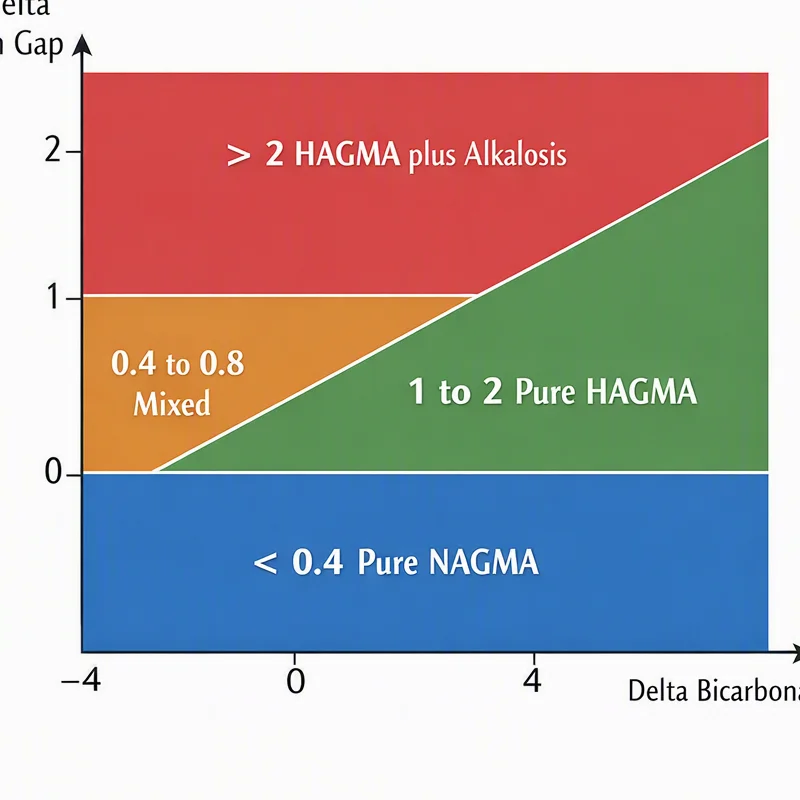
The delta gap is another useful concept. It compares the rise in anion gap with the fall in bicarbonate and helps identify mixed disorders. This can identify whether a patient has both a high-gap acidosis and another process, such as metabolic alkalosis or a normal-gap acidosis.
In clinical practice, the goal is not simply to describe a result as normal or abnormal. It is to use the result as part of laboratory interpretation that promotes a safer, more accurate diagnosis. That is why the anion gap is best viewed as one piece of a larger acid-base evaluation.
Correction of the Anion Gap for Low Albumin
Albumin correction is important when evaluating the anion gap in patients with low albumin. Since albumin is a primary unmeasured anion, a low level lowers the measured gap and can mask an underlying disorder.
When albumin is low, clinicians often estimate a adjusted anion gap. This adjustment can help bring back the result closer to what would be expected at a typical albumin level. Without this step, the value may remain within the apparent reference range even when clinically important acids are present.
A common approach is to raise the measured anion gap by a set amount for each decrease in albumin below normal. Different institutions may use slightly different formulas, so the exact method should follow local practice. The important point is that low albumin can lead to underestimation of the true acid burden.
This is especially pertinent in hospitalized patients, those with chronic illness, and patients undergoing critical care. In these settings, hypoalbuminemia is common and can alter both the interpretation and the urgency of further workup.
Stepwise Example Calculations
Below is a example computation using typical lab results. This illustrative calculation shows how the anion gap formula is used in routine use.
Example one: Basic calculation
Serum sodium = 140 mEq/L
Serum chloride = 102 mEq/L Serum bicarbonate = 24 mEq/LUsing the anion gap equation:
140 − (102 + 24) = 14
The anion gap is 14. If this is normal depends on the laboratory’s reference interval and whether potassium is included in the formula. If the result is near the upper end of the lab’s range, it may still be clinically acceptable, but the full context matters.
Example two: Elevated anion gap
Serum sodium = 138 mEq/L
Serum chloride = 100 mEq/L Serum bicarbonate = 14 mEq/L138 − (100 + 14) = 24
This is markedly elevated in many settings and may suggest an increased anion gap metabolic acidosis. Causes such as lactate-related acidosis, diabetic ketoacidosis, renal insufficiency, or toxic alcohol exposure should be considered.
Example 3: Albumin correction
Suppose the measured anion gap is 10 and albumin is low. After correcting for albumin, the albumin-corrected anion gap may rise into a higher range, revealing an abnormality that the uncorrected value missed. This is a common reason why albumin should always be reviewed when interpreting an electrolyte panel.
These examples show why the calculator is a first step, not the final answer. The number must be connected to symptoms, physical findings, and other testing.
Limitations and When Medical Review Is Needed
Although a carefully built calculator has boundaries. A spurious abnormal result can occur because of lab error, specimen issues, or recording errors. This is why unexpected results should be rechecked before making major decisions.
The anion gap is only one part of acid-base evaluation. It does not replace an blood gas study, a full electrolyte panel, or assessment of kidney function, glucose, lactate, and ketones when needed. It also does not identify the source of an abnormal result on its own.
Since interpretation affects healthcare decision-making, urgent symptoms should never be ignored. If a patient has severe weakness, confusion, rapid breathing, chest pain, dehydration, or altered mental status, prompt evaluation may be needed. In some cases, urgent care or emergency assessment is appropriate.
For anyone using an anion gap calculator as part of self-review or clinical screening, the best approach is to treat the result as a guide. If the number is unexpected, significantly high, or paired with concerning symptoms, professional review is important.
FAQ
What is an anion gap calculator used for?
An anion gap calculator is used to estimate the anion gap from blood test values and help assess acid-base balance. It is commonly used to screen for acid buildup, identify possible unmeasured acids, and support test interpretation of an electrolyte panel.
What is a normal anion gap range?
The normal anion gap depends on the laboratory’s normal range and whether potassium is included in the formula. In general, the result should be interpreted using the lab’s own reference interval rather than a single universal cutoff.
How do you calculate the anion gap from lab values?
Use the gap formula: sodium minus the sum of chloride and bicarbonate. In other words, anion gap = serum sodium − (serum chloride + serum bicarbonate). Some versions include potassium, but many calculators omit it.
Why does low albumin levels affect the anion gap?
Albumin is a negatively charged protein and a important unmeasured anion. When albumin is low, the measured anion gap may appear lower than it truly is. That is why albumin correction is necessary and why a corrected anion gap may be more reliable in patients with hypoalbuminemia.
What conditions can cause a high anion gap?
Common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. There may also be other causes, so the result should always be interpreted with the full clinical picture and, when appropriate, an arterial blood gas and other blood test results.