How to define the Anion Gap?
The anion gap is a figure obtained from a standard blood test that helps clinicians assess the level of electrolytes in the body. It is taken from a routine serum chemistry or electrolyte panel and is used to support review of acid-base balance. Although the term sounds highly specialized, the idea is straightforward: the result reflects the difference between measured positively charged ions and measured negatively charged ions in the blood.
This difference matters because it can reveal the presence of unmeasured anions or unmeasured cations that are not obvious from a basic panel alone. In clinical practice, the anion gap serves as a diagnostic tool and a quick way to guide result analysis when an acid-base disorder or other metabolic disturbance is suspected.
An anion gap calculator makes this process easier by using common lab values to calculate the result in seconds. But the number only becomes useful when you grasp what it means in medical context. A normal result may be encouraging, while an abnormal one can point toward issues such as metabolic acidosis, low albumin, or other conditions that call for further review.
Anion Gap Formula and Formula
The standard anion gap equation relies on measured values from the blood, specifically serum sodium, serum chloride, and serum bicarbonate. The standard anion gap formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some doctors use a modified form that includes potassium, but today’s calculators use the simpler version above because it is broadly accepted and handy for routine interpretation.
Here is the simple logic behind the equation:
- Sodium represents the main measured cation. Chloride and bicarbonate represent the primary measured anions. The gap shows the gap between measured positive and negative charges.
When you calculate the anion gap, you are not finding a gap in the literal sense. You are approximating the amount of charge carried by unmeasured substances in the blood. That is why the anion gap equation is so useful for identifying an acid-base disorder and for recognizing patterns in a serum chemistry result.
A elevated result suggests excess unmeasured acids or other compounds, while a lower-than-expected result can suggest a loss of negatively charged proteins or a measurement problem. Because of that, correct use of the anion gap formula depends on the complete lab picture, not just one isolated number.
How the Anion Gap Calculator Works
An anion gap calculator is designed to streamline the math and minimize manual errors. You input the input values from the electrolyte panel, and the calculator performs the calculation steps automatically. In most cases, you supply sodium, chloride, and bicarbonate values, then the tool returns the anion gap along with a reference range or interpretation note.
The process usually works like this:
- Provide the sodium value from the blood test. Provide the chloride value. Enter the bicarbonate value. Check the calculated result and assess it with the reference range.
Many users use an online calculator because it supports quick pattern recognition during result analysis. It is especially useful when reviewing an electrolyte panel in a busy clinical setting or when trying to understand whether a lab pattern suggests a broader metabolic issue.
Even though the calculator is simple, the numbers still need context. A value that falls within the reference range may still be abnormal if albumin is low or if another condition is changing the baseline. That is why the calculator is best viewed as a first step in interpretation, not the final answer.
In practical use, the calculator helps identify whether the result fits a typical normal anion gap pattern or whether further review is needed. It can also support decision-making when the goal is to understand possible causes of metabolic acidosis or other acid-base changes.
Normal Anion Gap Range and What Influences It
The expected range for the anion gap varies somewhat by laboratory because of variations in measurement methods, analyzer calibration, and reporting practices. This is where lab variation matters. A result that is deemed normal in one setting may be slightly different in another, so the lab’s own reference range should always be used first.
A few factors can affect the number:
- Albumin: Because albumin is a primary unmeasured anion, lower levels can decrease the measured gap. Lactate: Elevated lactate can raise the gap because it adds unmeasured anions. Lab variation: Different instruments and methods may yield slightly different values.
Albumin is especially important because it is one of the main contributors to the anion gap. When albumin is low, the normal anion gap may appear misleadingly normal. In those cases, an albumin correction or albumin adjustment may be needed to calculate a more accurate corrected anion gap.
That matters because a patient can have a serious acid-base problem even if the raw number seems normal. For that reason, interpreting the value without checking albumin can lead to missed findings. Similarly, elevated lactate can shift the result upward even before other abnormalities are obvious.
Raised Anion Gap: Frequent Causes
A raised anion gap usually points to the occurrence of unaccounted-for acids in the blood. The most common clinical concern is acidosis, where acid builds up or bicarbonate is used up in a way that raises the calculated gap.
Common causes include:
- Lactate acidosis, often related to reduced tissue oxygen delivery, severe illness, or decreased lactate clearance. Acid buildup from ketones, which can occur when ketone bodies build up during insulin deficiency, starvation, or other metabolic stress. Renal failure, where reduced acid excretion allows acids to persist. Toxic ingestion, including certain substances that generate unmeasured acids or interfere with normal metabolism.
This matters because they suggest different treatment pathways. For example, lactic acid buildup suggests a search for tissue hypoperfusion or severe infection, while ketoacidosis suggests abnormal fat metabolism and requires a different management approach. Renal failure may lead to acid retention over time, and toxin exposure can cause a dangerous metabolic picture that needs urgent assessment.
A high value is not a diagnosis by itself. It is a clue that should be considered alongside symptoms, history, and the rest of the blood test results. In many cases, it prompts further testing to identify the underlying cause and to determine how severe the metabolic disturbance is.
Reduced Anion Gap: Frequent Causes
A reduced anion gap is rarer than a high one, but it can still be medically significant. One of the most frequent explanations is hypoalbuminemia, because albumin is a negatively charged protein that contributes to the normal gap. When albumin falls, the calculated value can fall with it.
Other frequent causes include:
- Paraproteinemia, where abnormal proteins in the blood alter the balance of measured and unmeasured ions. Lab error, including specimen issues or measurement problems that distort the reported electrolytes.
Hypoalbuminemia is especially important because it can mask a serious condition if the result is interpreted without an albumin correction. In some patients, the corrected value may reveal a more significant disorder than the unadjusted number suggests. This is why a corrected anion gap can be more useful than the raw calculation alone.
Paraproteinemia should be considered when abnormal proteins are present, particularly if other findings do not match the apparent result. And because lab error is always possible, an unexpected low result should be reviewed carefully before drawing conclusions. Repeating the test or checking the full electrolyte panel may help confirm whether the number is real.
Clinical Role of the Anion Gap in Acid-Base Disorders
The anion gap is especially useful when used as part of a more comprehensive assessment of acid-base disorders. It helps distinguish different types of metabolic acidosis and strengthens the work of pattern recognition when reviewing a blood test, electrolyte panel, and serum chemistry results in combination.
In practice, the anion gap helps clarify questions such as:
- Is the acidosis related to accumulation of unmeasured acids? Might the pattern suggest bicarbonate loss instead? Is the gap elevated enough to justify looking for lactate, ketones, toxins, or renal dysfunction?
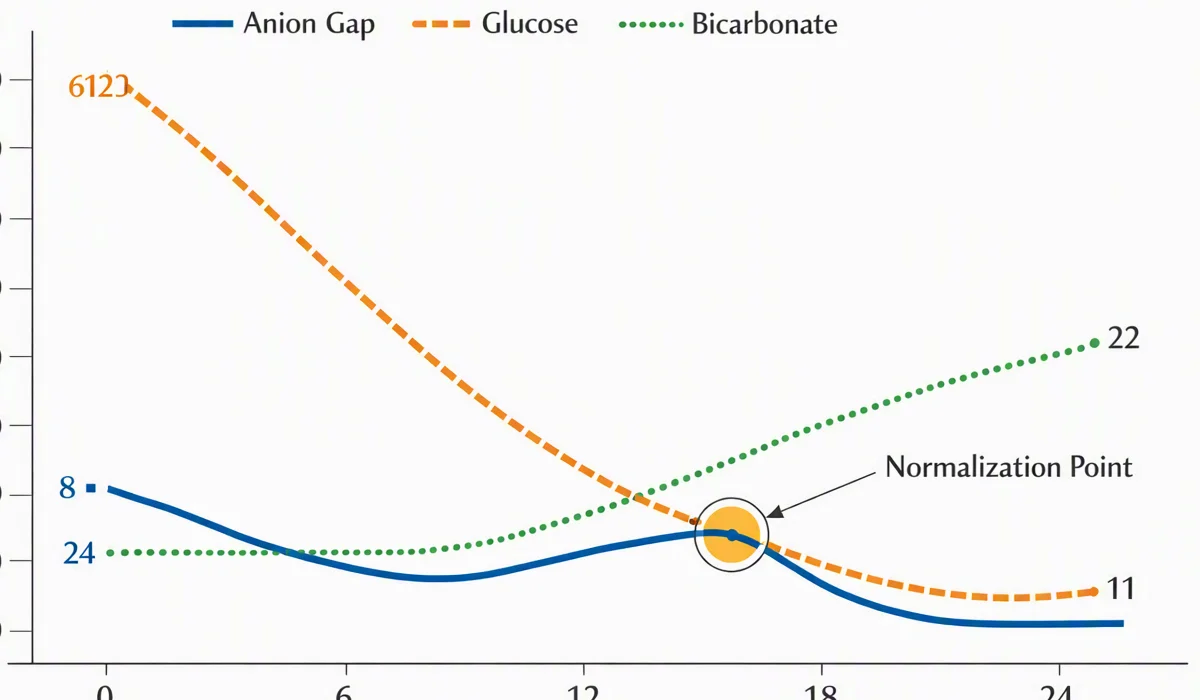
Another important concept is the delta gap, which compares the change in anion gap with the change in bicarbonate. This can help reveal mixed disorders, where more than one metabolic process is happening at the same time. That is useful because a anion gap clinical significance patient may have a high anion gap acidosis and another acid-base problem concurrently.
A blood gas is often interpreted alongside the anion gap to offer a fuller picture of acid-base status. The blood gas shows pH and respiratory compensation, while the anion gap helps identify the underlying metabolic component. Together, they improve clinical significance and help with cause assessment.
This is why the anion gap remains a valuable diagnostic tool: it turns a simple lab calculation into a meaningful guide for evaluating complex metabolic disturbances.
Ways to Interpret Outputs Safely
Good result interpretation requires more than just looking at a single value. The anion gap should be reviewed in the context of symptoms, the full electrolyte panel, medication history, kidney function, and any additional signs of illness. A result that appears abnormal may be explained by timing, fluid status, protein changes, or measurement differences.
Proper interpretation involves several steps:
- Verify the values used in the calculation. Check whether the lab’s reference range differs from other sources. Evaluate albumin and consider albumin adjustment if needed. Look for signs of electrolyte imbalance or metabolic acidosis. Find clinical clues that favor or reduce a suspected cause.
If the result suggests a significant problem, a medical evaluation is essential. This is especially true when symptoms step-by-step AG example such as confusion, rapid breathing, dehydration, vomiting, or severe weakness are present. The anion gap is useful, but it does not replace a full assessment of the person and the illness.
In other words, the number should inform the next step, not serve as the final conclusion. Combining the calculator result with clinical context improves accuracy and reduces the risk of missing an important problem.
FAQ
What is the anion gap calculator used for?
The anion gap calculator is used to calculate the anion gap from common blood test values, usually sodium, chloride, and bicarbonate. It helps with interpretation of acid-base balance and can point toward a metabolic disturbance such as metabolic acidosis.
What is the formula for calculating the anion gap?
The most common anion gap equation is: sodium minus the sum of chloride and bicarbonate. In short, the anion gap formula is sodium − (chloride + bicarbonate). Some versions may include potassium, but the simpler formula is widely used.
How is a normal anion gap result?
The normal range is influenced by the testing facility and analysis used, so the reference range on the lab report should be checked first. A result in the normal range generally suggests no major build-up of hidden acids, but low albumin and testing variation can affect the value.
What causes a high anion gap?
A increased anion gap is often due to acid buildup from problems including excess lactic acid, ketoacidosis, renal failure, or toxic ingestion. These causes contribute unmeasured acids to the blood and elevate the calculated value.
Could a low anion gap indicate a medical problem?
Yes, it can. A reduced anion gap can be associated with reduced albumin, protein abnormalities, or measurement error. It may also reflect other shifts in electrolytes or proteins, so it should be reviewed in clinical context rather than ignored.