An anion gap calculator is a helpful diagnostic tool for evaluating an acid-base disorder in pediatric patients. It enables clinicians interpret an electrolyte imbalance, recognize the likely cause of metabolic acidosis, and choose what additional testing may be needed. As pediatric patients have different physiology, growth patterns, and common illness patterns than adults, the clinical interpretation of the anion gap requires special attention to age, albumin, and the overall picture of lab values and symptoms.
Used properly, this simple calculation can reveal clues about unmeasured anions in the blood and support a broader metabolic evaluation. It is not a stand-alone diagnosis. Instead, it is part of a larger review of serum chemistry, the child’s condition, and any signs of an acidic state that may need urgent care.
How the Anion Gap Measures in Children
The anion gap is a calculated value that estimates the gap between measured positively charged and negatively charged particles in the blood. In practice, it is derived from serum sodium, serum chloride, and serum bicarbonate. This calculation formula is a way to detect an anion difference that may reflect extra acids or other unmeasured anions.
In children, the anion gap is especially valuable when evaluating metabolic acidosis. If the gap is elevated, it often implies the body has accumulated acids that are not directly measured on a basic electrolyte panel. If the gap is normal, the problem may be related to loss of bicarbonate or another process that does not increase unmeasured acids.
Understanding the buffer system matters here. The body maintains pH through coordinated changes in respiration, kidney function, and bicarbonate balance. When that system is disrupted, the anion gap can provide useful interpretive guidance about the direction of the problem. Still, the number itself must be viewed in context with the child’s symptoms, hydration status, and other blood chemistry findings.
How to Operate an Anion Gap Calculator
An anion gap calculator usually takes three inputs: sodium input, chloride value, and bicarbonate value. They are taken from a standard electrolyte panel or broader serum chemistry testing. The calculator then uses the standard formula to determine the anion gap.
The usual formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some laboratories use different versions that account for potassium, but the sodium-based formula is widely used for pediatric assessment because it is straightforward and consistent. The result should then be compared with the lab’s reference interval and the child’s clinical status.
To use the calculator effectively:
- Provide the most recent blood chemistry values from the same sample when possible. Look for obvious data entry errors before relying on the result. Assess whether the child has signs of dehydration, infection, or another condition that changes acid-base balance. Interpret the number alongside the bicarbonate level, not in isolation.
The calculator is best thought of as a quick screen for an acid-base disorder. It does not take the place of clinical reasoning or a full differential diagnosis. In pediatric care, the real value is in relating the calculation to the child’s symptoms, exam findings, and other lab values.
Child Reference Ranges and Normal Values
A reference range for children for the anion gap may differ slightly by laboratory, developmental stage, and measurement technique. A anion gap within normal range does not mean the child is free of illness, and an out-of-range result does not always mean disease. It simply provides a clue that must be considered carefully.
Young patients may have age-based variations in serum chemistry because renal function, overall body water, diet, and illness patterns shift during development. Babies, children, and adolescents may all show small differences in electrolytes and acid-base balance. For this reason, local reference values are important.
Laboratory variation also matters. Different analyzers and measurement methods can alter the reported result. A number that appears mildly elevated in one lab may be considered normal in another. That is why pediatric interpretation should always use the local reference interval and not rely on a single universal cutoff.
In general, the anion gap is used as a screening tool rather than a definitive diagnostic endpoint. A mildly different value may reflect normal biologic variation, while a larger abnormality suggests a more notable acid-base problem that should be evaluated further.
Adjusting the Anion Gap for Albumin
Serum albumin serves as a major unmeasured negatively charged ion in blood. When albumin is low, the measured anion gap may look falsely normal or only mildly elevated even when an acid load is present. This is why albumin correction is so important in pediatric care.
Hypoalbuminemia can occur with illness, inflammation, poor nutrition, kidney disease, or fluid shifts. In these situations, the uncorrected number may underestimate the severity of the problem. Calculating a corrected anion gap offers a better estimate of the true acid burden and improves the accuracy of the clinical interpretation.
While formulas may vary, the principle is consistent: if albumin is low, the gap should be adjusted upward to account for the missing negative charge. This is frequently termed the albumin-adjusted gap. The correction is especially important when evaluating a child with a suspected acid-base disorder but a less dramatic anion gap than expected.
Using the corrected result promotes better diagnostic reasoning. It can help distinguish a truly normal gap from one that only appears normal because of low albumin. In a child with metabolic acidosis, that distinction can change the differential diagnosis and the next steps in care.
Increased metabolic acidosis with a high anion gap in Pediatrics
High anion gap metabolic acidosis means there is a buildup of acids or acid precursors that are not directly measured in the standard electrolyte panel. This is a major reason clinicians use the anion gap calculator in pediatrics. It helps narrow the differential diagnosis and can reveal potentially urgent conditions.
Frequent pediatric causes include lactic acidosis, ketoacidosis, and renal insufficiency. These conditions increase unmeasured acids in the blood, decreasing bicarbonate and increasing the gap. In children, lactic acidosis may occur with poor perfusion, severe infection, or shock. Ketoacidosis can occur with diabetes, prolonged fasting, or other states of poor carbohydrate utilization. Renal failure impairs the body’s ability to excrete acid, resulting in accumulation.
Other uncommon causes also belong in the differential diagnosis, especially if the presentation is severe or unexpected. A child with an elevated gap may need urgent evaluation for toxin exposure, tissue hypoxia, or inherited metabolic disorders depending on the history and exam.
When the gap is high, the next question is not just “How high is it?” but “Why is it high?” This question guides further testing, treatment priorities, and the level of monitoring needed.
Typical Anion Gap Acid-Base Acidosis in Pediatrics
Normal-gap metabolic acidosis is often termed hyperchloremic acidosis because chloride commonly increases as bicarbonate drops. The anion gap remains in the expected range, but the child still has delta ratio calculation tool metabolic acidosis. For this reason a normal result should not be dismissed if the clinical picture suggests an acid-base problem.
Two common pediatric causes are diarrhea and tubular kidney acidosis. With diarrhea, the body loses bicarbonate through the gastrointestinal tract, leading to base loss. In renal tubular acidosis, the kidneys fail to appropriately reclaim bicarbonate or excrete acid, so acid builds up without a large increase in unmeasured anions.
Because the anion gap stays normal, recognition depends on combining the calculation with the bicarbonate level and the overall clinical picture. A child with continued loose stools, limited feeding, or growth concerns may have a normal-gap acidosis that is easy to miss without careful review of the electrolyte panel.
This is where pediatric assessment matters. A normal gap is not reassuring if the child appears unwell, dehydrated, or acidotic. It simply points clinicians toward a different mechanism of acid-base disruption.
Frequent Causes, Key Signs, and Subsequent Measures
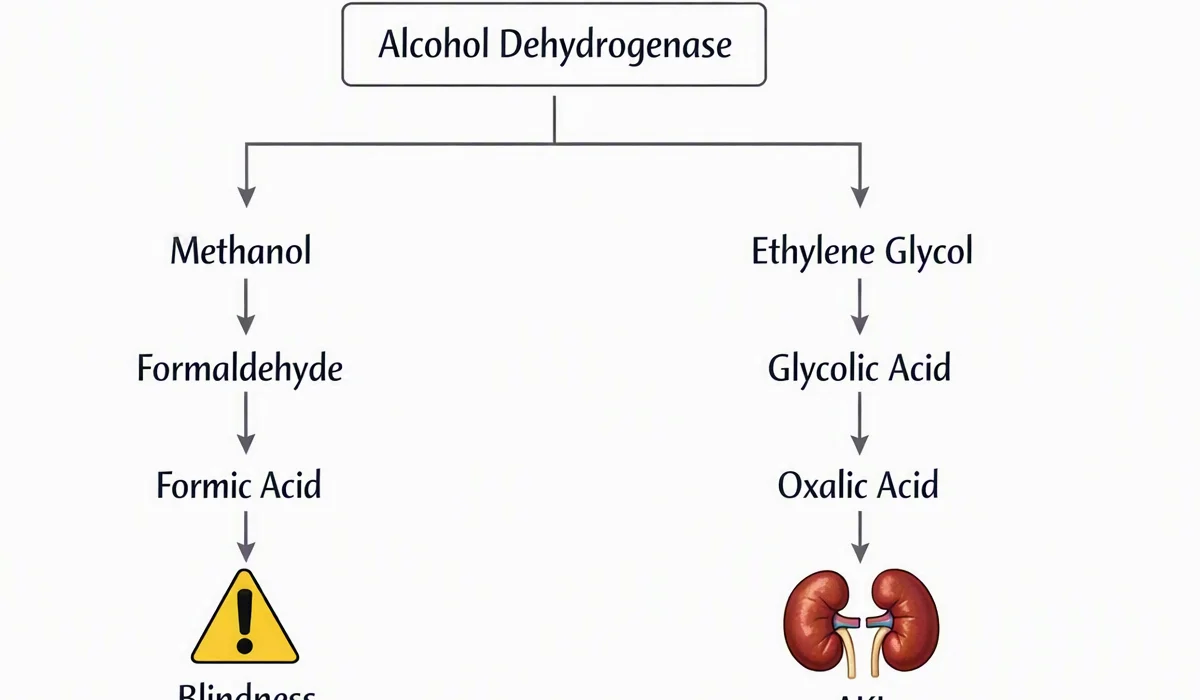
Many frequent pediatric illnesses can affect the anion gap and should be considered during interpretation. Toxic substance exposure is one important cause of high-gap acidosis, especially when the history is unclear or the child has sudden neurologic changes. Sepsis can lead to lactic acidosis through poor tissue perfusion and systemic inflammation. Dehydration may concentrate labs and worsen acid-base imbalance, especially when accompanied by vomiting, diarrhea, or poor intake.
An arterial blood gas can be extremely helpful when the electrolyte panel suggests a problem but the severity is uncertain. It provides a direct look at pH, carbon dioxide, and bicarbonate status, helping confirm whether the child truly has metabolic acidosis and whether respiratory compensation is present.
Subsequent steps depend on the clinical setting. In a stable child, repeat testing and careful history may be enough. In a child who appears toxic, lethargic, or severely dehydrated, urgent evaluation is needed. Additional studies may include glucose, lactate, ketones, kidney function tests, toxicology testing, and infection workup. The anion gap is best used as part of a broader metabolic evaluation rather than as a stand-alone answer.
Drawbacks of Anion Gap Calculation in Children
Although useful, the anion gap has important limitations in pediatric interpretation. One major issue is multiple acid-base abnormalities. A child may have more than one process at the same time, such as vomiting plus sepsis, which can make the gap harder to interpret. In such cases, a “normal” value may hide a significant disturbance, or a high value may reflect combined processes rather than a single cause.
Testing error is another concern. Pre-analytic issues, sample handling problems, or transcription mistakes can distort serum sodium, serum chloride, or serum bicarbonate values. Even small errors can shift the calculated result enough to mislead clinical reasoning.
The albumin effect is especially important in children with sickness, inflammation, or inadequate intake. If serum albumin is low, the raw number may understate the true acid burden. That is why a revised result can be more informative than the raw value alone.
Finally, pediatric interpretation requires careful context. Developmental stage, illness severity, hydration, kidney function, and medication exposure all affect blood chemistry. A value should not be interpreted in isolation from the child’s symptoms, exam, and additional testing.
Used wisely, the anion gap calculator strengthens strong diagnostic reasoning. Used alone, it can mislead. The best approach is to consider the calculation as one part of a thoughtfully combined clinical picture.
Frequently Asked Questions
What is the normal anion gap in pediatric patients?
The pediatric reference range for the anion gap depends on the laboratory method and the child’s age, so there is no universal value. In general, clinicians check the result with the lab’s stated normal range and consider whether serum albumin is low, because hypoalbuminemia can make the gap look smaller than expected.
How do you calculate the anion gap in children?
The standard anion gap calculation uses serum sodium minus the sum of serum chloride and serum bicarbonate. This calculation formula is commonly built into an anion gap calculator and is usually applied to values from the same electrolyte panel for reliable clinical interpretation.
Why should albumin be considered when interpreting the anion gap?
Serum albumin is a major unmeasured anion, so low albumin can obscure an elevation in the gap. Using an albumin correction helps calculate the corrected anion gap and reduces the risk of missing an acid-base disorder in a child with hypoalbuminemia.
What causes a raised anion gap metabolic acidosis in pediatrics?
Typical reasons of high anion gap metabolic acidosis in children include lactic acidosis, ketoacidosis, and renal failure. Other notable possibilities include toxic ingestion, sepsis, and other conditions that elevate unmeasured acids in the blood.
Is a normal anion gap ever linked to
Absolutely. A child can have normal anion gap metabolic acidosis when bicarbonate is lost or acid handling is impaired without accumulation of unmeasured anions. Typical examples include diarrhea and renal tubular acidosis, both of which can cause bicarbonate loss and true metabolic acidosis despite a normal gap.