What the Anion Gap Measures
The anion gap is a derived measurement that helps clinicians analyze electrolytes and recognize indicators of metabolic acidosis. It reflects the connection between measured cations and measured anions in the serum chemistry panel, mainly using sodium, chloride, and bicarbonate. Because not all charged particles are directly measured, the anion gap offers indirect insight into unmeasured anions and broader acid-base disorders.
In practical terms, an elevated or reduced anion gap can guide clinical assessment when reviewing an electrolyte panel. It supports acid-base interpretation by helping clinicians recognize whether the body is building up acids, depleting bicarbonate, or dealing with another metabolic derangement. This makes the anion gap especially useful in laboratory interpretation, where small patterns can point toward important diagnoses.
The concept is simple: the gap estimates the difference between what is measured and what is expected in the bloodstream. When the balance shifts, the result can suggest an electrolyte imbalance or a disorder that calls for more focused evaluation. In that sense, the anion gap serves as a quick form of diagnostic support that fits naturally into a larger diagnostic workflow.
How to Operate an Anion Gap Calculator
An anion gap calculator is a practical utility for rapid calculation during emergency evaluation, ward review, or internal medicine assessment. It helps clinicians enter key lab values and produce an answer without manual arithmetic, reducing the chance of error during busy decision-making. Most calculators rely on sodium, chloride, and serum bicarbonate, and some also permit inclusion of potassium.
To use the calculator, input the patient’s measured lab values from the chemistry panel. The result can then be compared with the expected reference interval or local reference range. A value outside the usual range may prompt further clinical assessment for metabolic acidosis, a hidden acid load, or a relevant electrolyte abnormality.
Including potassium is optional in many settings. Some formulas leave out it because potassium is present in much lower concentration than sodium, but other clinicians prefer the potassium-inclusive version for a more complete picture of anion concentration. What matters most is consistency: follow the same method when trending results over time.
The calculator is most helpful when combined with the rest of the chart. For example, if the serum bicarbonate is low, the anion gap can help differentiate a true high-gap process from a normal-gap disorder. If the pattern is unexpected, the calculator becomes part of a broader laboratory interpretation workflow rather than a stand-alone answer.
Formula and Common Variations for Anion Gap
The standard anion gap formula is typically written as:
anion gap = sodium − (chloride + bicarbonate)
With potassium added, the formula becomes:
anion gap = sodium + potassium − (chloride + bicarbonate)
These equations approximate the difference between measured positive and negative ions in the blood. The outcome offers a useful screen for hidden acids and other unmeasured anions. In many clinical settings, the potassium-free formula is favored because it is easier and widely used in routine serum chemistry reporting.
A corrected anion gap is often necessary when albumin is abnormal. Albumin is a major unmeasured anion, so low albumin can make the apparent gap look falsely normal or low. This is why albumin correction is crucial when interpreting results in patients with malnutrition, chronic illness, liver disease, or inflammation.
The idea of a normal anion gap depends on the assay used by the laboratory and the local reference range. Different analyzers and methods can yield slightly different values, so clinicians should read the result in context rather than rely on one universal cutoff. A calculator that incorporates the correct laboratory method improves diagnostic support and lowers misclassification.
Reading Increased Anion Gap Findings
A raised reading often indicates high anion gap metabolic acidosis. In this case, the body has built up acids that are not separately measured on the chemistry panel, causing the calculated gap to increase. This picture frequently reflects clinically important metabolic acidosis and requires prompt attention, especially when accompanied by symptoms, hemodynamic instability, or worsening mental status.
One major cause is lactic acidosis, where lactate rises because of tissue hypoperfusion, sepsis, hypoxemia, seizures, or severe physiologic stress. Another common cause is ketoacidosis, which may develop in diabetes, starvation, or alcohol-related illness. In both cases, the calculator helps measure the acid-base pattern and aids faster clinical decision support.
Renal failure is another classic contributor. When kidney function declines, acids are retained and normal buffering capacity is reduced. The result can be a rising anion gap along with other changes in the metabolic profile. In these cases, the calculator helps distinguish kidney-related acid retention from other causes of acid-base disorders.
High-gap results should always be interpreted with the full clinical picture. A single number does not diagnose the underlying disorder, but it can strengthen the case for urgent risk stratification, additional labs, blood gas testing, and a focused review for toxic exposures, ischemia, or severe dehydration. Used this way, the calculator becomes a useful part of clinical assessment rather than just a mathematical tool.
Interpreting Normal or Reduced Anion Gap Results
A normal anion gap metabolic acidosis often points to reduced bicarbonate or poor acid excretion without a significant increase in unmeasured acid compounds. Frequent examples include gastrointestinal bicarbonate loss and certain renal tubular problems. In this setting, the calculator remains valuable because a normal gap can refine the differential instead of ending the evaluation.
A reduced anion gap is uncommon, but it should not be ignored. The leading explanation is hypoalbuminemia, since reduced albumin lowers the pool of unmeasured anions. This can hide a clinically important disturbance if the result is not adjusted with a proper corrected anion gap. In patients with chronic disease or poor nutritional status, albumin correction is often essential.
Another important cause is laboratory error. Sample problems, analyzer issues, contamination, or transcription mistakes can produce misleading results. If the number does not fit the clinical picture, repeat testing is appropriate before making major decisions. A low or unexpectedly normal result should also prompt review of the overall electrolyte pattern and the patient’s acid-base status.
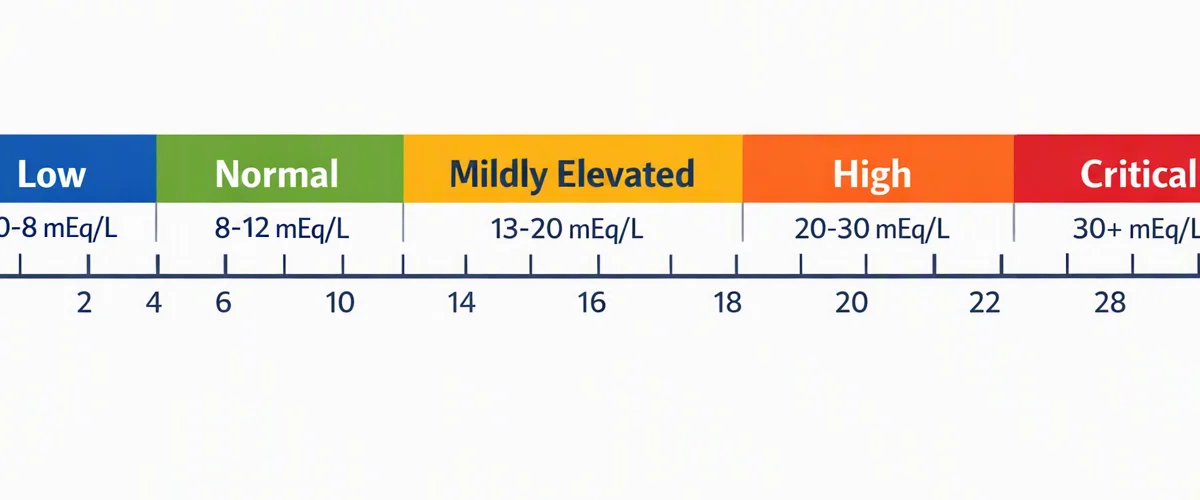
Because the anion gap is derived from measured values, small analytic differences can have a greater effect than expected. This is why clinicians should compare the number against the laboratory’s reference range and review trends over time. A normal gap does not always mean the patient is stable, and a low value can sometimes be the earliest clue to a broader laboratory or physiologic issue.
Medical Clinical Decision Support Use Cases
The anion gap is a helpful component of clinical decision support because it converts standard chemistry data into actionable information. In emergency medicine, it supports rapidly identify high-risk patients with unexplained metabolic acidosis. In critical care, it aids serial monitoring of acid-base status and supports monitor response to treatment over time.
As an example, a patient with altered mental status, hypotension, or tachypnea may have a subtle acid-base problem that is not apparent from the chart alone. A fast anion gap calculator result can direct the next step in the diagnostic workflow, whether that means checking lactate, ketones, kidney function, or a blood gas. This is where the tool offers genuine diagnostic support rather than simple educational value.
In routine inpatient care, the calculator can assist differentiate whether a falling bicarbonate reflects a high-gap process or a normal anion gap disorder. That distinction matters because it guides the differential diagnosis and determines what additional workup is needed. When integrated into daily review of the electrolyte panel, the calculator supports more reliable laboratory interpretation and more assured decision-making.
The anion gap is also useful in risk stratification. A rising gap may signal worsening illness even before symptoms become pronounced. Likewise, a low or corrected-normal value can comfort clinicians that the apparent disorder is less severe than it first appeared, provided the rest of the assessment is concordant.
Limitations, Traps, and Best Practices
A key limitation is the need for albumin correction. Because albumin is a major unmeasured anion, low levels can hide an elevated gap. If not corrected, the clinician may underestimate the severity of the disorder. Always check albumin when the anion gap seems out of line with the patient’s presentation.
Another common pitfall is overreliance on a single reference range. Multiple laboratories use different analyzers and reporting conventions, so a result should be interpreted in the context of the local assay. A value that seems abnormal in one setting may be within the expected interval in another. For that reason the best practice is to use the calculator with the laboratory’s own reporting framework.
A mixed acid-base disorder can also cloud interpretation. A patient may have both a high-gap process and a second disturbance that partially offsets it, making the bicarbonate or pH seem less abnormal than expected. In these cases, the calculator is only one part of the analysis and should be paired with blood gas data, clinical context, and serial trends.
Repeat testing is appropriate when the result Visit this site conflicts with the clinical picture or when there is concern for laboratory error. Rechecking the chemistry panel can avoid misclassification and unnecessary treatment. Best practice is to review sodium, chloride, bicarbonate, potassium, and albumin together, then interpret the result within the broader picture of acid-base disorders and the patient’s overall condition.
You get the best results by using the anion gap as part of a structured review: confirm the lab values, assess albumin, consider the reference range, and then connect the pattern to the likely diagnosis.
FAQs About the Anion Gap Calculator
What is an anion gap calculator used for?
An anion gap calculator is used to aid clinical decision support by quickly estimating the anion gap from routine lab values. It helps clinicians assess metabolic acidosis, identify possible unmeasured acids, and organize the differential for acid-base disorders. It is especially useful during chart review, emergency assessment, and ongoing laboratory monitoring.
How do you calculate the anion gap from lab values?
The most common anion gap formula is sodium − (chloride + bicarbonate). Some versions also include potassium, using sodium + potassium − (chloride + bicarbonate). The calculator uses the patient’s lab values from the chemistry panel to perform a fast, accurate gap calculation.
Why do you correct the anion gap for albumin?
You correct the anion gap for albumin because albumin is a major unmeasured anion. If albumin is low, the measured gap may look incorrectly normal or low. A corrected anion gap gives a more accurate picture of the true acid-base status, especially in patients with hypoalbuminemia.
What does a high anion gap mean clinically?
A high result suggests high anion gap metabolic acidosis, which often reflects accumulation of acids such as lactate or ketones. Common causes include lactic acidosis, ketoacidosis, and renal failure. The finding should prompt additional clinical evaluation rather than be interpreted in isolation.
Can a normal anion gap still indicate a serious disorder?
Yes. A normal anion gap can still occur in significant illness, including normal anion gap metabolic acidosis. It may also be seen when a high-gap process is masked by hypoalbuminemia or when a mixed disorder is present. That is why clinicians should consider the full clinical context, the serum bicarbonate, and the possibility of laboratory error before concluding the evaluation.