What the Anion Gap Shows in DKA
The anion gap is a laboratory-derived value that helps determine the reason of metabolic acidosis. In diabetic ketoacidosis, it is especially useful because it suggests the accumulation of acids that are not directly measured on a standard chemistry panel. This renders the anion gap a practical diagnostic tool for recognizing high anion gap metabolic acidosis.
An anion gap calculator calculates the difference between the major measured cations and anions in the blood. The result helps clinicians review serum chemistry data in the context of the patient’s acid-base balance. In DKA, the gap elevates as ketones build up and contribute unmeasured anions to the bloodstream.
Because DKA is an acidotic state, the body typically shows a low bicarbonate level along with an elevated anion gap. That pattern reflects ketone accumulation and a wider metabolic derangement. The anion gap does not diagnose DKA by itself, but it helps reinforce the diagnosis and tracks how the condition is shifting over time.
How to Operate an Anion Gap Calculator
An anion gap calculator uses a set of a few basic lab values from the electrolyte panel. You provide the serum sodium, serum chloride, and serum bicarbonate values, and the calculator applies the calculator formula to produce the result.
The basic workflow is straightforward:
- Collect the latest serum sodium value. Obtain the serum chloride value. Collect the serum bicarbonate value from the serum chemistry panel. Add the values into the calculator. Review the result alongside the rest of the laboratory results and clinical assessment.
This is important because DKA evaluation hardly ever depends on one number alone. The anion gap is part of a broader lab interpretation process that includes the patient’s symptoms, glucose level, ketone testing, pH, and treatment response. A calculator simplifies the math, but interpretation still demands clinical judgment.
Many clinicians rely on the result as a fast screen for metabolic acidosis and as a marker of resolution of acidosis during treatment monitoring. As the underlying ketoacidosis improves, the anion gap should trend toward normal and eventually show anion gap closure.
Anion Gap Formula and Normal Ranges
The classic anion gap formula anion gap clinical significance is:
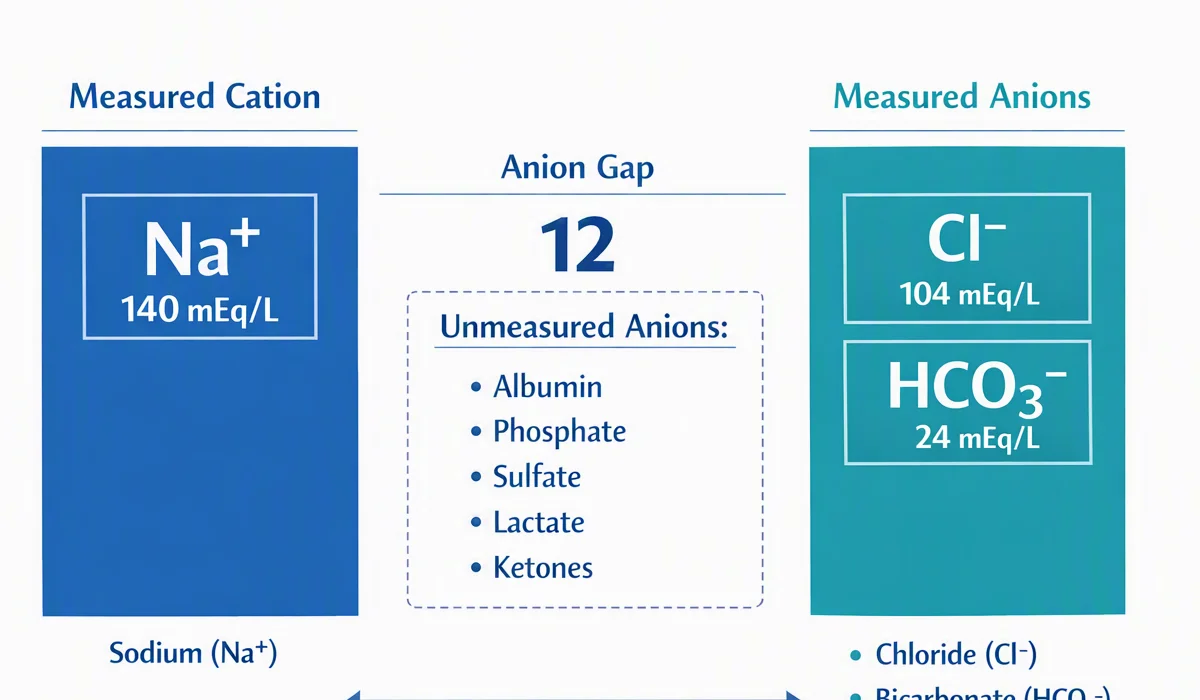
Anion gap = Sodium − (Chloride + Bicarbonate)
Using this formula, the calculator calculates the relationship between measured ions in the blood. Sodium is the main measured cation, while chloride and bicarbonate are the main measured anions included in the formula. Any additional acids in the blood are often represented indirectly as unmeasured anions.
The normal anion gap range changes a bit depending on the laboratory method and the reference range used by that lab. That variation is why it is important to read the number in context rather than rely on a single universal cutoff. A mildly different result may still be normal if the lab’s reference interval differs.
In practice, the anion gap should be considered with the rest of the electrolytes and with awareness of albumin correction. Albumin is a negative protein that affects the gap, so lower albumin can make the gap appear falsely low or normal. That is a key reason a raw value may not tell the full story.
Why the Anion Gap Is Elevated in DKA
In DKA, insulin deficiency leads to increased fat breakdown and production of ketones, especially acetoacetate and beta-hydroxybutyrate. These acids enter the bloodstream as unmeasured anions, which raises the anion gap and contributes to ketoacidosis.
The process is a clear disturbance in acid-base balance. As ketones accumulate, they consume bicarbonate, decreasing the bicarbonate level and causing a metabolic acidosis with a high anion gap. This pattern is a typical hallmark of DKA and helps distinguish it from other forms of acidosis.
Beta-hydroxybutyrate is commonly the dominant ketone in severe DKA, so the degree of ketosis may be more pronounced than a urine ketone test suggests. That is why the anion gap and direct ketone testing are complementary. Together, they show the patient’s acid burden more accurately than either test alone.
Correcting the Anion Gap for low albumin
Albumin strongly influences the measured anion gap because it is a significant unmeasured anion in blood. When albumin is low, the anion gap may be too low. This is why albumin correction is often advised, especially when the clinical picture suggests acidosis but the raw gap seems less striking than expected.
Hypoalbuminemia can occur in many hospitalized patients and can mask a true high-gap process. In that setting, a corrected anion gap gives a more accurate picture of the patient’s metabolic state. The corrected value helps avoid missing DKA or downplaying the degree of acid accumulation.
Although formulas for albumin correction can be slightly different, the goal is the same: modify the gap based on the measured serum albumin so the value better reflects the true acid burden. This matters because a normal-looking gap can be misleading if albumin is low. In DKA workups, the corrected value can improve lab interpretation and support more precise treatment monitoring.
Other Labs to Evaluate Together with the Anion Gap
The anion gap is only one part of the DKA workup. A careful evaluation also involves blood glucose, ketone body measurement, and acid-base testing. These studies support the diagnosis of the diagnosis and guide management.
An arterial blood gas or venous blood gas can show the pH and bicarbonate level, which indicate how severe the acidemia is. While venous testing is often adequate in many settings, the choice depends on the clinical context. Either way, the pH helps identify the acidotic state and adds to the differential diagnosis.
Beta-hydroxybutyrate is especially useful because it directly reflects ketone burden. It can demonstrate ketone accumulation even when other markers are less clear. Blood glucose is also essential, but a normal or only mildly elevated glucose does not rule out DKA, especially in euglycemic presentations.
Reviewing these findings together produces a more complete picture of the metabolic derangement. The anion gap, blood gas, glucose, and ketones should be viewed as a group rather than as isolated laboratory results.
How the Anion Gap Changes During DKA Treatment
Treatment of DKA typically includes insulin administration and intravenous fluids. As insulin suppresses ketone production and fluids enhance circulation and renal clearance, the anion gap should progressively fall. This trend is among the clearest signs that treatment is working.
During treatment monitoring, the clinician looks for anion gap closure, which suggests that the major ketoacid burden is resolving. The gap may normalize before the bicarbonate fully recovers, so it is important to look at the entire pattern rather than one value alone.
Checking electrolytes is vital during this phase. Potassium, sodium, chloride, and bicarbonate can shift quickly as therapy progresses. IV fluids and insulin can also change the apparent acid-base profile, so serial labs are needed to ensure true improvement rather than a temporary lab shift.
As treatment continues, the goal is not only to improve glucose but also to correct the underlying acidosis. The anion gap helps show whether the ketoacid production has stopped and whether the body is moving toward a stable acid-base balance.
Frequent Mistakes & Reading Errors
A frequent mistake is not recognizing a mixed acid base disorder. Someone with DKA may also have nausea and vomiting, impaired respiratory compensation, or another metabolic process that changes the expected pattern. In those cases, the anion gap may not tell the whole story by itself.
Testing error is another issue. A single incorrect sodium, chloride, or bicarbonate result can skew the calculated gap and lead to incorrect conclusions. If the number does not fit the clinical picture, it is reasonable to repeat testing and assess the full electrolyte panel.
Chloride-related acidosis can develop during or after DKA treatment, especially after large volumes of chloride-containing fluids. This can lower the bicarbonate while the anion gap normalizes, making the metabolic picture look hard to interpret. In that setting, the persistent acidosis may be due to chloride rather than ongoing ketone production.
Serum albumin also matters here. If albumin is low and not accounted for, the gap may appear falsely reassuring. Careful lab interpretation requires awareness of the corrected value, the clinical assessment, and the treatment timeline.
When a Normal Anion Gap Is Not Enough to Exclude DKA
A normal anion gap does not completely exclude DKA. One important example is euglycemic DKA, where the blood glucose may be normal or only mildly elevated despite active ketoacidosis. This can happen in certain medication contexts or with reduced carbohydrate intake, and it requires a high index of suspicion.
Another reason the gap may look normal is that β-hydroxybutyrate can remain elevated even when other markers are less dramatic. In early or partially treated disease, the anion gap may also begin to improve before the full metabolic picture resolves. That is why clinical assessment is so important.
If the patient still has symptoms and there is ongoing acidosis on blood gas testing, DKA can still be present even when the gap is not clearly elevated. In that setting, the differential diagnosis should include DKA, mixed disorders, and other causes of acidosis. The anion gap is valuable, but it is not a standalone rule-out test.
Common Questions
What is the anion gap in diabetic ketoacidosis?
The anion gap in diabetic ketoacidosis is a calculated lab value that helps identify high anion gap metabolic acidosis. It rises because ketones accumulate as unmeasured negative ions, lowering bicarbonate and increasing the gap. It is used to support diagnosis and follow improvement during treatment.
How is the anion gap calculated from lab values?
Apply the anion gap calculator or use the anion gap formula: sodium minus the combined chloride and bicarbonate values. The required values are blood sodium, chloride level, and serum bicarbonate. The result should be interpreted with the rest of the serum chemistry and clinical findings.
What is the normal anion gap range for adults?
The expected anion gap range depends on the laboratory’s reference interval and testing method. Since ranges can differ, the best approach is to compare the result with the lab’s stated normal limits rather than relying on one universal number. Albumin level can also affect what looks normal.
Why do you correct the anion gap for albumin?
You correct the anion gap for serum albumin because low albumin can make the gap appear falsely low or normal. In low albumin, the measured value may underestimate the degree of acidosis. Albumin correction helps produce a more accurate albumin-corrected anion gap for lab interpretation.
Can diabetic ketoacidosis happen with a normal anion gap?
Yes. Euglycemic DKA, early treatment, low albumin, or a combined acid-base disorder can make the gap appear normal even when DKA is still present. If symptoms, ketones, pH, and bicarbonate point to ongoing disease, the diagnosis should still be considered AG significance in acidosis even with a normal gap.