How the Anion Gap Evaluates
The anion gap is a practical way to estimate the discrepancy between measured cations and measured anions in serum chemistry. In routine acid-base analysis, it helps clinicians identify whether an electrolyte imbalance is being caused by unmeasured anions rather than by the ions typically reported on a lab panel. This makes it a valuable diagnostic tool for sorting out a metabolic disturbance.
At its core, the anion gap represents the relationship between sodium concentration, chloride concentration, and bicarbonate level. Because the body must maintain acid-base balance, shifts in electrolytes can indicate a broader acid-base disorder. That is why the anion gap is often reviewed alongside other laboratory values rather than used alone.
The concept is based on the fact that plasma remains electrically neutral, even though not all ions are measured directly. The reported numbers show an anion-cation difference that indirectly reveals the presence of acids, proteins, and other charged particles. In clinical practice, this is especially useful when the serum bicarbonate is low and the source of the acid load needs further evaluation.
Because the anion gap is an estimate rather than a direct count, it is best viewed as a preliminary measure with strong screening utility. It does not diagnose a specific disease by itself, but it narrows the differential diagnosis and supports clinical interpretation in a patient with suspected metabolic problems.
How the Anion Gap Calculator Works
An anion gap calculator uses standard lab inputs to perform a quick calculation formula that estimates the gap from sodium, chloride, and bicarbonate. The usual formula is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
This formula compares the key measured cation, serum sodium, with the primary measured anions, serum chloride and serum bicarbonate. The result is used during acid-base analysis to assess whether there are extra acids in the blood that are not directly shown on the panel.
Some labs use a variation that includes potassium, but the sodium-based form is the most prevalent in clinical review. The calculator is highly valuable because it removes manual arithmetic errors and gives immediate support for clinical evaluation. It is often applied after reviewing a basic metabolic panel or an electrolyte panel.
For example, if the serum sodium is 140, serum chloride is 104, and serum bicarbonate is 24, the gap is 12. That number may sit within the expected reference range, depending on the laboratory’s methodology. The result then informs next steps in evaluating the patient’s acid-base disorder and overall metabolic disturbance.
Because the formula depends on measured lab inputs, the calculator is only as reliable as the numbers used. A small change in sodium, chloride, or bicarbonate can shift the result and influence severity assessment. That is why the tool should be used with the full clinical picture, not as a standalone answer.
Normal Anion Gap Range & Interpretation
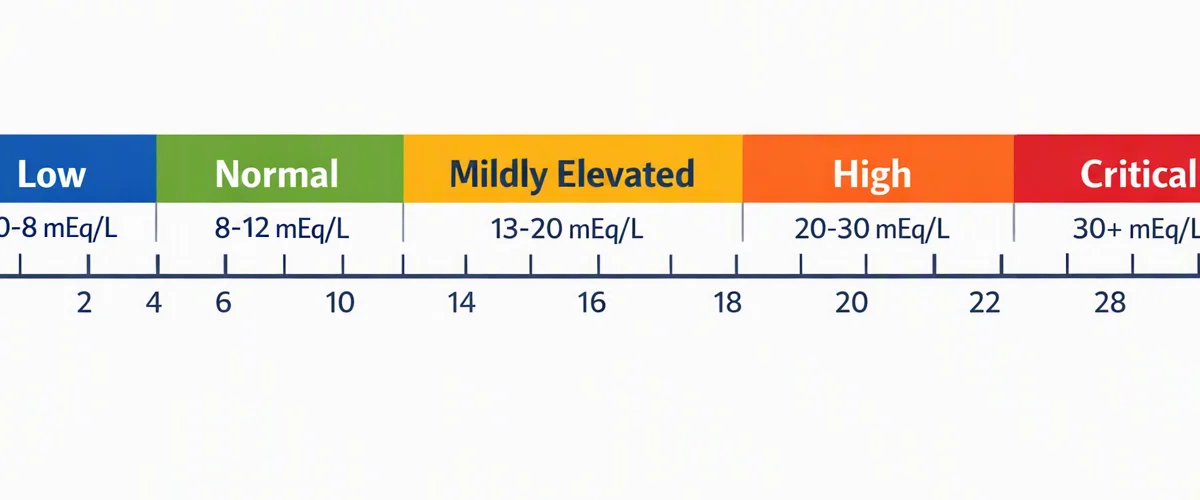
The reference range for the anion gap varies by laboratory because of varied analyzers, reporting methods, and reference materials. In most settings, the normal interval is narrow enough that a result above it suggests a elevated anion gap, while a result within it may indicate a typical anion gap pattern. The exact number must always be read in relation to the lab’s own normal range.
Clinical interpretation begins with determining whether the gap is elevated, normal, or unexpectedly low. A increased anion gap often indicates accumulation of acids or other unmeasured particles. A normal gap does not exclude a serious acid-base problem, but it shifts attention toward bicarbonate loss or chloride gain rather than excess acid production.
Albumin is a major contributor to the gap because it behaves as an unmeasured anion. When reduced albumin is present, the measured anion gap may appear falsely low or normal even when there is significant acid accumulation. That is why a raw result must be reviewed carefully, especially in hospitalized or critically ill patients.
In practical terms, the same numeric value can mean different things in different contexts. A gap that is normal by one lab’s standards may be borderline high by another lab’s reference range. This is why the calculator should be paired with the laboratory’s specific reference range and the patient’s acid-base status.
Reasons of High Anion Gap Metabolic Acidosis
Acidic metabolic state with a high anion gap typically reflects accumulation of acids that consume bicarbonate and leave behind excess anions. This remains one of the key uses of the anion gap calculator in practical acid-base analysis. The result helps clinicians distinguish a classic high-gap pattern from other forms of acidosis.
Lactate-related acidosis is a common cause and occurs when lactate builds up due to tissue hypoperfusion, shock, severe infection, seizures, or other states of increased anaerobic metabolism. Because lactate is an unmeasured negative ion, the gap rises as bicarbonate falls. In this setting, the anion gap supports recognition of a serious metabolic problem that needs urgent attention.
Ketone-induced acidosis is another major cause, seen in diabetes, starvation, or alcohol-related metabolic stress. Ketone bodies act as unmeasured charged particles that increase the gap while lowering serum bicarbonate. The pattern can be especially useful when laboratory findings and symptoms suggest an acid load but the cause is not yet obvious.
Renal failure can also produce a high gap because the kidneys are unable to clear organic acids efficiently. As acids accumulate, the anion gap rises and bicarbonate declines. Other causes may include toxins, severe dehydration, or marked tissue breakdown, but lactic acidosis, ketoacidosis, and renal failure are among the most important clinically.
In high-gap states, the calculator helps frame the question: is the patient dealing with excess acid production, impaired acid excretion, or another source of metabolic disturbance? That question directs the next steps in evaluation and treatment.
Reasons of Typical Anion Gap Metabolic Acidosis
A normal-gap finding, sometimes called nonanion gap acidosis, usually means bicarbonate has been removed and replaced by chloride. The total gap stays near the usual range, but the disorder is still present. The key clue is often a decreased bicarbonate with a relatively elevated chloride, a pattern known as chloride excess.
Diarrhea is a classic cause because the gastrointestinal tract can lose base-rich fluid. As bicarbonate falls, chloride rises to maintain electrical balance, producing a non-gap acidosis. In this case, the calculator helps verify the pattern but does not identify the source on its own.
Tubular acidosis is another important reason. Here, the kidneys fail to process acid or bicarbonate properly, leading to ongoing acidosis with a normal gap. Different subtypes can present with specific electrolyte findings, but the overall clue remains the same: a decreased bicarbonate with unchanged gap size.
High chloride itself is often part of the mechanism because chloride replaces lost bicarbonate in the serum. This is why checking chloride values alongside the anion gap is essential. A normal-gap acidosis can be missed if the clinician focuses only on the gap and not on the full electrolyte panel.
Recognizing a normal-gap pattern is important because treatment is different from high-gap acidosis. The calculator supports the distinction, but the underlying cause must be determined through history, examination, and further laboratory testing.
How to Adjust the Anion Gap for Albumin
Albumin is among the main unmeasured anions in the blood, so variations in serum albumin can substantially alter the anion gap. When hypoalbuminemia is present, the gap may miss the severity of acidosis. This is why albumin correction is often recommended in acid-base assessment.
The corrected anion gap adjusts the measured value upward when albumin is low. Many correction methods exist, but the goal is the same: compensate for the loss of negative charge from albumin so the result better matches the true acid burden. This is a practical form of gap correction that improves clinical interpretation.
A common approach is to apply a fixed amount for each decrease in serum albumin below normal. The exact formula may differ by institution, but the principle remains stable. If albumin is reduced, the uncorrected number may appear deceptively normal, masking a high anion gap process.
Correcting for albumin is especially helpful in critical illness, liver disease, malnutrition, or any setting where protein levels may be altered. In these cases, the anion gap calculator should be paired with serum albumin so the interpretation captures the patient’s actual acid-base state. Without that step, the clinical picture may be less accurate.
In short, hypoalbuminemia can conceal a clinically meaningful rise in acids. Albumin correction helps uncover that risk and increases the accuracy of the corrected anion gap during routine review.
Anion Gap, Delta Gap, and Mixed Disorders
The delta gap calculation and delta-delta relationship are advanced tools for identifying a mixed acid-base pattern. Once a high anion gap acidosis has been found, these calculations help assess whether another disorder is present at the same time. This is especially useful when the patient’s numbers do not match a single pattern neatly.
The delta gap compares the rise in the anion gap with the fall in bicarbonate. The bicarbonate change is used to see whether bicarbonate has fallen proportionally to the gap increase. If the values do not align with expected behavior, a second acid-base process may be present, such as metabolic alkalosis or an additional non-gap acidosis.
The delta-delta calculation is another way to evaluate the relationship between change in the anion gap and change in bicarbonate. A ratio outside the expected pattern can suggest a hidden mixed disorder. This matters because a patient may have lactic acidosis plus diarrhea, or ketoacidosis plus vomiting, and the combined findings can obscure the overall picture.
Using delta calculations enhances clinical reasoning because it goes beyond identifying whether the gap is high. It asks whether the acid-base disorder is isolated or combined. That distinction can shape treatment decisions, fluid choice, and the urgency of further testing.
For practical acid-base analysis, the sequence is often: measure the anion gap, decide if it is high or normal, and then apply delta methods if the pattern suggests more than one disturbance.
Using an Anion Gap Calculator in Clinical Review
An anion gap calculator is particularly valuable when anion gap clinical significance interpreting a basic metabolic panel, arterial blood gas, or electrolyte panel in a patient with potential acidosis. These results supply the core numbers needed to calculate the gap and judge whether the result fits the clinical picture. The calculator is an efficient way to support clinical evaluation when time matters.
It becomes especially valuable when the arterial blood gas shows a decreased bicarbonate or low pH and the cause is not clear. The calculator can help identify whether the process is a elevated anion gap disorder or a typical anion gap process. That distinction narrows the differential diagnosis and helps direct further testing.
In everyday practice, the tool is also helpful for reviewing a potential electrolyte disturbance, following changes over time, or checking whether treatment is resolving the underlying metabolic problem. Because lab numbers can shift rapidly, repeated use may help with ongoing severity assessment and trend tracking.
This calculator must not substitute for professional judgment. Instead, it should serve as part of a careful evaluation that includes symptoms, medication review, fluid status, and other laboratory values. Under those conditions, it offers strong screening utility and helps organize the diagnostic process.
Limitations and Frequent Calculation Mistakes
Even though its usefulness, the anion gap has important limitations. Test variability can change the apparent result because different analyzers and methods generate slightly different values. A number that looks abnormal on one report may fall within the expected reference range on another.
Erroneous measurements can also affect the outcome. Since the formula depends on serum sodium, serum chloride, and serum bicarbonate, even slight measurement differences can shift the outcome. This is one reason the result should be interpreted in the context of the full clinical picture rather than as a standalone value.
Technology used in testing is important too. Ion-selective electrodes are widely used to test electrolytes, but they are still vulnerable to interference or method differences. Such analytical factors can affect the reported chloride or sodium and thereby affect the final gap.
Another limitation is the presence of unmeasured ions. The anion gap is osmolar and anion gap combined an estimate, not a direct count of every charged particle in plasma. If unusual substances are present, the calculation may downplay or overstate the true problem. This is why the tool is best used as a guide for additional acid-base analysis, not as the final answer.
Frequent mistakes include ignoring albumin, using the wrong reference range, or failing to consider a mixed disorder. The most reliable approach is to pair the calculation formula with the patient’s symptoms, acid-base status, and complete chemistry results.
FAQs
Why is an anion gap calculator used?
An anion gap calculator is used to assist with acid-base analysis by estimating whether there is a hidden acid load in the blood. It helps distinguish metabolic acidosis with a high anion gap from a normal anion gap pattern and improves clinical interpretation of laboratory values.
What counts as a normal anion gap?
The normal values depend on the laboratory’s reference range or reference interval. Because different analyzers report slightly different results, the most accurate answer is the one listed by the specific lab. A result within that range usually suggests a normal anion gap, while a higher value may indicate a high anion gap.
How do you calculate the anion gap from lab values?
The common calculation formula is: serum sodium − (serum chloride + serum bicarbonate). This uses serum sodium, serum chloride, and serum bicarbonate to estimate the gap. An anion gap calculator automates the math and makes the process faster during clinical review.
Why correct the anion gap for albumin?
You correct the anion gap for albumin because hypoalbuminemia can leave the measured gap seem falsely normal or low. Since albumin is a major unmeasured anion, albumin correction helps uncover the true corrected anion gap and supports interpretation in acid-base disorders.
What does a high anion gap indicate in acid-base analysis?
A high anion gap in acid-base analysis usually indicates accumulation of unmeasured anions from a process such as lactic acidosis, ketoacidosis, or renal failure. It is a indicator to metabolic acidosis and should prompt review of the patient’s labs, symptoms, and possible mixed disorders.