What Is the Anion Gap?
The anion gap is a straightforward yet helpful value derived from routine electrolytes on a serum chemistry panel. It assists clinicians in identifying hidden acids or other unmeasured anions that may be affecting a patient’s chemistry. In practical terms, the anion gap value supports clinical interpretation of blood chemistry by showing whether there may be an underlying electrolyte imbalance or metabolic acid-base disorder.
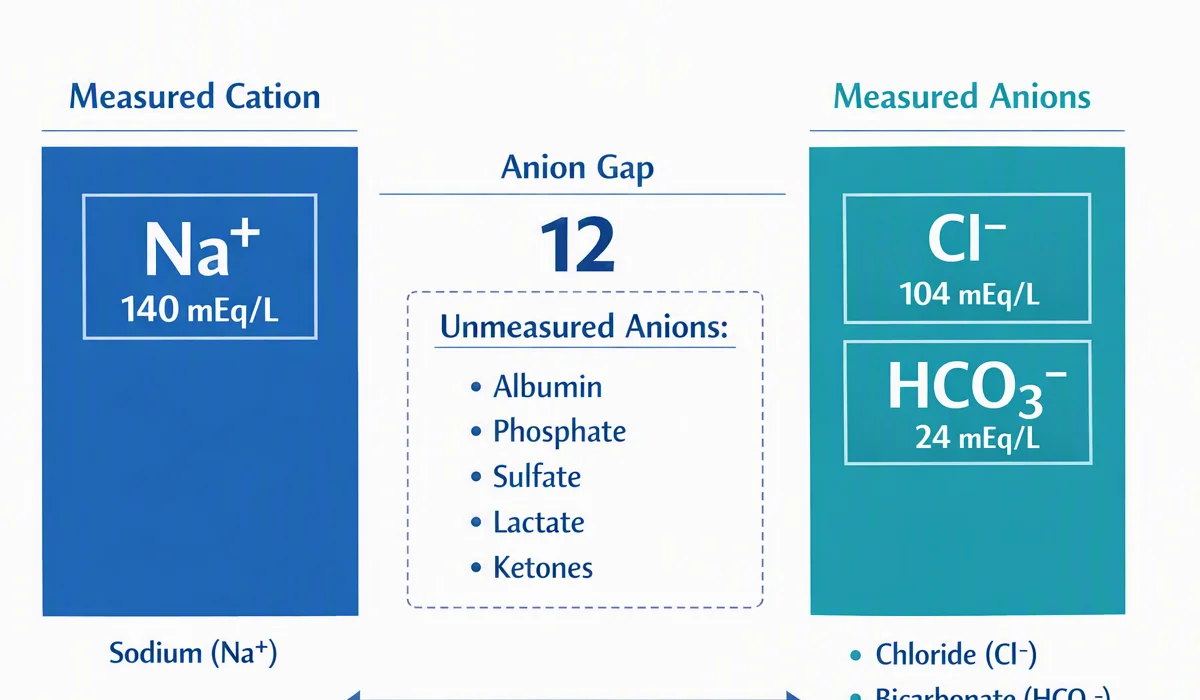
The classic anion gap formula relates positively charged ions with negatively charged ions, most commonly using serum sodium, serum chloride, and serum bicarbonate. In many lab systems, potassium may also be included, although the most common version excludes it. The result is not a direct measurement of acid, but a diagnostic aid that can point toward conditions that require more detailed acid-base evaluation.
Because the anion gap is calculated from standard laboratory results, it is widely used in bedside and outpatient patient assessment. A considered interpretation of the number can suggest whether there is a high anion gap pattern, a normal anion gap state, or an unexpectedly low anion gap that deserves confirmation.
Why the Refined Anion Gap Is Important
This usual anion gap is helpful, but it can be misleading when albumin is decreased. Because serum albumin holds a substantial amount of negativity in the blood, hypoalbuminemia can lower the measured gap even when clinically important acids are present. For this reason the corrected anion gap matters: it calibrates the number so the clinician can better judge acid-base balance.
In the absence of albumin adjustment, a patient with substantial metabolic acidosis may appear to have a normal result. That is especially important in hospitalized or critically ill patients, where albumin may decline because of inflammation, poor nutrition, fluid shifts, or illness severity. In these situations, the corrected value strengthens diagnostic interpretation and promotes more accurate decisions.
The corrected result is not meant to override clinical judgment. Instead, it adds context to the raw calculation and improves clinical significance. For example, a “normal” anion gap in a patient with low albumin may still conceal a true acid load. This is why correction is often a better reflection of real physiology than the unadjusted number alone.
How the Anion Gap Calculator Operates
The Anion Gap Calculator simplifies the anion gap calculation so healthcare providers and students can quickly calculate the gap from routine blood chemistry. Most calculators apply a clear calculation formula based on serum sodium, serum chloride, and serum bicarbonate. In its usual form, the calculation is:
anion gap = sodium - (chloride + bicarbonate)Some versions also add potassium, which modestly changes the result. A potassium-inclusive formula may be written as:
anion gap = sodium + potassium - (chloride + bicarbonate)Both versions are applied in practice, but the sodium-based formula is the most common. The calculator does not diagnose disease by itself; it is a diagnostic aid that helps assess the broader pattern of blood chemistry. When paired with the patient’s presenting features, pH, lactate, ketones, kidney function, and medication history, it becomes part of a complete clinical interpretation.
Because the anion gap represents the difference between measured cations and measured anions, it indirectly signals the presence of unmeasured anions. That is why it is so valuable in detecting metabolic problems that might otherwise be overlooked on a standard serum chemistry panel.
Adjusting the Anion Gap for Albumin
The adjusted anion gap takes into account the influence of serum albumin. As albumin is a important negatively charged protein, reduced levels can make the gap seem falsely low or within range. The albumin correction adjusts the number upward when albumin is below the normal reference range.
A common correction approach adds a fixed amount for each gram per deciliter that albumin is below the usual level. Some institutions may use slightly different formulas, so the exact adjustment may vary. In general, the lower the albumin, the greater the need for adjustment. This is the practical heart of gap correction.
Why is this important? Because reduced albumin can mask a true metabolic acidosis. A patient may have a standard anion gap that looks normal, yet the corrected value reveals a clinically significant elevation. That difference can change the workup, the urgency of treatment, and the interpretation of the overall acid-base balance.
Reviewing the corrected result is particularly important when comparing values against a lab’s reference interval. A “normal” uncorrected number may no longer be normal after adjusting for albumin. For this reason, the corrected calculation is often a more accurate reflection of the patient’s true clinical meaning than the raw value alone.
Frequent Causes of an Elevated Anion Gap
An raised gap commonly suggests presence of acid compounds or unmeasured negative ions. The main contributors include lactate acidosis, ketotic acidosis, renal failure, and specific toxic ingestions. These states can each disturb acid base balance and show a distinct high anion gap pattern.
Lactate acidosis can develop when tissues are not adequately perfused or struggling metabolically, leading to increased lactate production. Ketone acidosis occurs when ketone bodies rise, often in diabetes, alcohol-related illness, or prolonged fasting. Renal failure can raise the gap because the kidneys are unable to eliminate acids effectively.
Toxic alcohols are another significant cause of raised values. Ingestions involving methanol, ethylene glycol, and related compounds can produce serious acid-base derangements that may be life-threatening. Salicylate drugs can also alter the pattern, sometimes creating a mixed disorder that requires careful review of the full clinical picture.
Because these disorders can overlap, the anion gap should be viewed as a single part of the puzzle. It supports clinical interpretation, but it does not replace history, exam, medication review, and targeted testing. The calculator is most useful when it helps determine the following step in the diagnostic process.
How to Interpret Normal or Low Anion Gap Results
A low anion gap is not as common than an elevated one, but it can still be important. Before concluding there is a problem, the first question is whether the result is accurate. Testing error is one of the most common explanations, so repeating the sample is often the first step if the result is unanticipated.
A normal anion gap does not always mean there is not any acid-base disorder. If the patient has hypoalbuminemia, the true gap may be too low until an albumin correction is applied. That is why the adjusted result can be more helpful than the initial number when assessing metabolic acidosis.
Another important cause of a low or unexpectedly normal result is paraproteinemia. Abnormal proteins can alter the blood chemistry pattern and affect the apparent balance of measured ions. In such cases, the anion gap is not a diagnosis by itself, but a hint that may prompt further workup.
When interpreting low or normal results, consider the entire clinical interpretation: albumin level, other electrolytes, pH, bicarbonate, kidney function, and the patient’s symptoms. This broader approach strengthens diagnostic interpretation and helps avoid false reassurance.
Stepwise Sample Calculation
Here is a simple worked example based on typical laboratory values. Suppose the patient has the following:
- serum sodium: 140 chloride level: 102 serum bicarbonate: 18 potassium level: 4.0
Using the usual sodium-based formula, the calculation is:
anion gap = 140 - (102 + 18)This results in an anion gap of 20. If the lab’s reference range is lower than that, this may indicate a increased anion gap. If the patient also has low serum albumin, the next step is albumin adjustment to determine the corrected anion gap.
At this point assume the albumin is reduced. After applying the appropriate anion gap correction, the corrected value may be even higher, revealing a more significant metabolic problem than the unadjusted number suggested. For this reason the Anion Gap Calculator is a highly practical assessment tool: it simplifies the math while retaining the clinical meaning.
This worked example also shows how the result connects to the rest of the evaluation. A high gap with low bicarbonate can support concern for acidic state, while the underlying cause may be lactic acidosis, ketone buildup, kidney failure, alcohol toxins, or aspirin-related compounds. The calculator does not identify the cause, but it assists in narrowing the differential.
FAQs About Corrected Anion Gap Results
What is a corrected anion gap and why is it used?
The corrected anion gap is the standard anion gap modified for low serum albumin. It is used because hypoalbuminemia can make the uncorrected value look artificially low. The correction improves clinical interpretation and more accurately shows the patient’s true acid-base balance.
How is calculated the anion gap with albumin correction?
albumin corrected anion gap low albuminStart with the usual anion gap formula using serum sodium, serum chloride, and serum bicarbonate. Then add an albumin correction based on the measured serum albumin. The exact method may change by institution, so the calculator should follow the same reference range and formula used by the lab or clinical setting.
What does a high anion gap?
A high anion gap commonly suggests extra acids in the blood, such as in lactic acidosis, ketoacidosis, renal failure, or exposure to toxic alcohols or salicylates. It is a key clue in the evaluation of metabolic acidosis, but it should be interpreted with the rest of the laboratory results and the patient’s symptoms.
Can a normal anion gap still mean a serious problem?
Yes. A normal anion gap does not always rule out clinically important illness. Hypoalbuminemia can hide a true gap, and a lab error can also distort the result. In addition, a patient may have another type of metabolic problem that requires broader acid-base evaluation and clinical review.
When should an anion gap result be reviewed by a clinician?
Any unexpected result should be reviewed when it does not fit the patient’s condition, especially if there is metabolic acidosis, altered mental status, kidney dysfunction, suspected poisoning, or significant electrolyte imbalance. The result is best used as a diagnostic aid within overall patient assessment, not as a standalone answer.