What Is the Anion Gap?
The anion gap is a basic but valuable value derived from routine electrolytes on a serum chemistry panel. It helps medical professionals detect hidden acids or other unmeasured anions that may be affecting a patient’s chemistry. In practical terms, the anion gap value supports clinical interpretation of blood chemistry by showing whether there may be an underlying electrolyte imbalance or metabolic acid-base disorder.
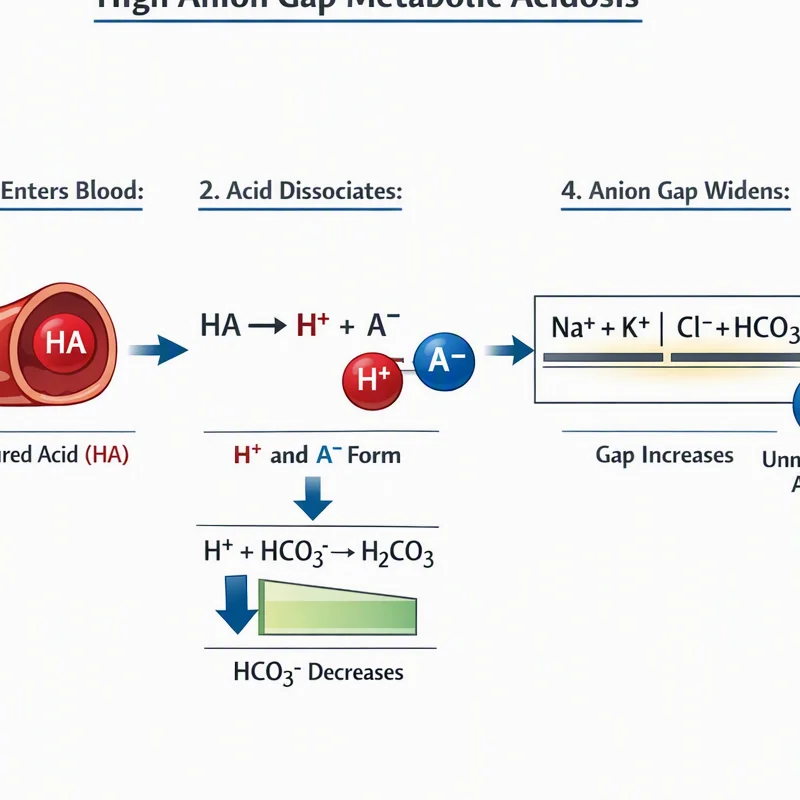
The classic anion gap formula compensates positively charged ions with negatively charged ions, most commonly using serum sodium, serum chloride, and serum bicarbonate. In many lab systems, potassium may also be included, although the most common version excludes it. The result is not a direct measurement of acid, but a diagnostic aid that can indicate conditions that require more detailed acid-base evaluation.
Because the anion gap is calculated from standard laboratory results, it is widely used in bedside and outpatient patient assessment. A careful review of the number can suggest whether there is a high anion gap pattern, a normal anion gap state, or an unexpectedly low anion gap that deserves confirmation.
How the Adjusted Anion Gap Matters
The standard anion gap is valuable, but it can be deceptive when albumin is low. Since serum albumin holds a significant amount of negativity in the blood, hypoalbuminemia can reduce the measured gap even when relevant acids are present. This is why the corrected anion gap is important: it calibrates the number so the clinician can more accurately judge acid-base balance.
In the absence of albumin adjustment, a patient with marked metabolic acidosis may seem to have a comforting result. This is especially important in hospitalized or critically ill patients, where albumin may fall because of inflammation, poor nutrition, fluid shifts, or illness severity. In these settings, the corrected value strengthens diagnostic interpretation and promotes more accurate decisions.
The corrected result is not meant to substitute for clinical judgment. Instead, it supplies context to the raw calculation and improves clinical significance. For example, a “normal” anion gap in a patient with low albumin may still hide a true acid load. This is why correction is often a truer reflection of real physiology than the unadjusted number alone.
How the Anion Gap Calculator Operates
The Anion Gap Calculator simplifies the anion gap calculation so medical professionals and students can quickly calculate the gap from routine blood chemistry. Most calculators rely on a clear calculation formula based on serum sodium, serum chloride, and serum bicarbonate. In its common form, the calculation is:
anion gap = sodium - (chloride + bicarbonate)Some versions also incorporate potassium, which slightly changes the result. A potassium-inclusive formula may be written as:
anion gap = sodium + potassium - (chloride + bicarbonate)Both versions are used in practice, but the sodium-based formula is the most familiar. The calculator does not confirm disease by itself; it is a diagnostic aid that helps read the broader pattern of blood chemistry. When paired with the patient’s symptoms, pH, lactate, ketones, kidney function, and medication history, it becomes part of a full clinical interpretation.
Because the anion gap represents the difference between measured cations and measured anions, it indirectly indicates the presence of unmeasured anions. That is why it is so useful in detecting metabolic problems that might otherwise be undetected on a standard serum chemistry panel.
Correcting the Anion Gap for Albumin
The adjusted gap reflects the impact of serum albumin. As albumin is a major negatively charged protein, decreased levels can make the gap appear falsely low or within range. The correction for albumin raises the number upward when albumin is below the normal normal range.
A standard correction approach applies a fixed amount for each gram per deciliter that albumin is below the usual level. Some institutions may use slightly different formulas, so the exact adjustment may vary. In general, the lower the albumin, the greater the need for recalculation. This is the practical heart of gap correction.
Why does this matter so much? Because hypoalbuminemia can mask a true metabolic acidosis. A patient may have a standard anion gap that looks unremarkable, yet the corrected value reveals a clinically meaningful elevation. That difference can change the workup, the urgency of treatment, and the interpretation of the overall acid-base status.
Interpreting the corrected result is particularly important when comparing values against a lab’s normal range. A “normal” uncorrected number may no longer be normal after albumin correction. For this reason, the corrected calculation is often a more reliable reflection of the patient’s true clinical meaning than the raw value alone.
Common Causes of an Elevated Anion Gap
An elevated gap commonly indicates build-up of acid compounds or uncounted anions. The main causes are elevated lactate, ketotic acidosis, kidney failure, and specific toxic exposures. These conditions can each disturb acid base balance and create a clear increased anion gap pattern.
Elevated lactate can develop when tissues are not adequately perfused or struggling metabolically, leading to higher lactate production. Ketotic acidosis arises when ketone bodies rise, often in diabetes, alcohol-related illness, or prolonged fasting. Renal insufficiency can raise the gap because the kidneys are unable to clear acids effectively.
Alcohol toxins are another significant cause of elevated values. Ingestions involving methanol, ethylene glycol, and related compounds can produce severe acid-base derangements that may be life-threatening. Salicylate drugs can also alter the pattern, sometimes creating a mixed disorder that requires careful review of the full clinical picture.
Because these disorders can overlap, the anion gap should be viewed as an element of the puzzle. It supports clinical assessment, but it does not replace history, exam, medication review, and targeted testing. The calculator is most useful when it directs the next action in the diagnostic process.
How to Understand Normal or Low Anion Gap Results
A low anion gap is less common than an increased result, but it can still matter. Before thinking it indicates illness, the first question is whether the result is genuine. Laboratory error is one of the most frequent explanations, so checking the sample again is often the first step if the result is unexpected.
A regular anion gap does not always mean there is not any acid-base disorder. If the patient has hypoalbuminemia, the true gap may be underestimated until an albumin correction is applied. That is why the adjusted result can be more helpful than the initial number when considering metabolic acidosis.
Another important cause of a reduced or unexpectedly normal result is paraproteinemia. Abnormal proteins can distort the blood chemistry pattern and change the apparent balance of measured ions. In such cases, the anion gap is not a diagnosis by itself, but a signal that may prompt further workup.
When interpreting low or normal results, take into account the entire clinical interpretation: albumin level, other electrolytes, pH, bicarbonate, kidney function, and the patient’s symptoms. This broader approach improves diagnostic interpretation and helps reduce false reassurance.
Stepwise Illustrative Calculation
Here is a simple sample calculation with standard laboratory values. Let’s say the patient has the following:
- blood sodium: 140 blood chloride: 102 blood bicarbonate: 18 blood potassium: 4.0
With the common sodium-based formula, the calculation is:
anion gap = 140 - (102 + 18)This yields an anion gap of 20. If the lab’s expected range is lower than that, this may indicate a high anion gap. When the patient also has low albumin level, the next step is adjusting for albumin to determine the corrected anion gap.
Now assume the albumin is reduced. Following applying the appropriate anion gap adjustment, the corrected value may be even higher, revealing a more significant metabolic problem than the unadjusted number suggested. For this reason the Anion Gap Calculator is a highly practical clinical tool: it simplifies the math while corrected AG app retaining the clinical meaning.
That sample calculation also shows how the result connects to the rest of the evaluation. A high gap with low bicarbonate can support concern for acid-base imbalance, while the underlying cause may be lactate buildup, ketone buildup, renal insufficiency, alcohol toxins, or aspirin-related compounds. The calculator does not identify the cause, but it assists in narrowing the differential.
Frequently Asked Questions About Corrected Anion Gap Results
What exactly is a corrected anion gap and why is it used?
The anion gap adjusted for albumin is the regular anion gap corrected for low serum albumin. It is used because hypoalbuminemia can make the uncorrected value look artificially low. The correction strengthens clinical interpretation and more accurately shows the patient’s true acid-base balance.
How do you calculate the anion gap with albumin correction?
Start with the usual anion gap formula using serum sodium, serum chloride, and serum bicarbonate. Then use an albumin correction based on the measured serum albumin. The exact method may change by institution, so the calculator should follow the same reference range and formula used by the lab or clinical setting.
What may suggest a high anion gap?
A high anion gap commonly suggests extra acids in the blood, such as in lactic acidosis, ketoacidosis, renal failure, or exposure to toxic alcohols or salicylates. It is a key clue in the evaluation of metabolic acidosis, but it should be interpreted with the rest of the laboratory results and the patient’s symptoms.
Can a normal anion gap still mean a serious problem?
Yes. A anion gap clinical significance normal anion gap does not always rule out clinically important illness. Hypoalbuminemia can hide a true gap, and a lab error can also distort the result. In addition, a patient may have another type of metabolic problem that requires broader acid-base evaluation and clinical review.
When should an anion gap result be reviewed by a clinician?
Any unexpected result should be reviewed when it does not fit the patient’s condition, especially if there is metabolic acidosis, altered mental status, kidney dysfunction, suspected poisoning, or significant electrolyte imbalance. The result is best used as a diagnostic aid within overall patient assessment, not as a standalone answer.